• HAVE YOU SEEN OR EXPERIENCED THE IMPACT OF DEI OR RADICAL GENDER IDEOLOGY AT YOUR INSTITUTION? CLICK HERE TO SHARE YOUR STORY.
Do No Harm
  • About Us
    • ABOUT
    • TEAM
    • FAQS
    • WHAT OTHERS SAY
    • VOICES OF DO NO HARM
  • OUR WORK
    • NEWSROOM
    • ISSUE AWARENESS
      • IDENTITY POLITICS (DEI)
      • GENDER IDEOLOGY
    • POLICY WORK
    • LEGAL ACTION
    • RESEARCH
    • RESOURCES
    • CENTERS
  • GET INVOLVED
    • SUBMIT A TIP
    • BECOME A MEMBER
    • CAREERS
    • INTERNSHIPS
    • IMPACT
  • MEDIA INQUIRIES
  • Search
  • DONATE
  • Menu Menu
img_16533

Open Letter to Daniel Wechsler, MD, PhD, President of the American Society of Pediatric Hematology/Oncology

COMMENTARY Georgia DEI Medical association Commentary Kurt Miceli, MD

Dear Dr. Wechsler,

I write to you today in my capacity as chief medical officer of Do No Harm, an organization dedicated to promoting merit, fairness, and excellence in healthcare and healthcare education. With over 54,000 members, including pediatric hematologists/oncologists, we are focused on keeping identity politics out of medicine. We seek an end to divisive and unscientific trends in medicine, such as “Diversity, Equity, and Inclusion” (DEI) and youth-focused gender ideology.

To that end, we have seen decisive actions taken on the part of both federal and state governments. These actions include the presidential executive order “Ending Illegal Discrimination and Restoring Merit-Based Opportunity,” which makes clear that illegal DEI policies “undermine our national unity, as they deny, discredit, and undermine the traditional American values of hard work, excellence, and individual achievement in favor of an unlawful, corrosive, and pernicious identity based spoils system.” Likewise, your home state of Georgia has been a leader on these issues, particularly in academia, by ending diversity statements in hiring at public universities, promoting diversity of thought, and making clear that “[e]qual opportunity and decisions based on merit are fundamental values of the University System of Georgia.”

Similarly, we believe medical societies — and their leadership — have a critical obligation to bring an end to divisive DEI practices. Given your installation as president of the American Society of Pediatric Hematology/Oncology (ASPHO), you lead an organization of 2,000 members whose mission is to “support and empower the pediatric hematology and oncology medical and scientific community.” Undoubtedly, this mission reflects the profound impact ASPHO members make every day in advancing research, education, and compassionate care for young patients and their families. We hope that under your leadership ASPHO will take the necessary steps to renew its focus on excellence — a standard its members expect and its patients deserve.

There is work to be done. ASPHO has unfortunately continued to prioritize DEI to its own detriment, replacing merit with identity considerations. This is evident on ASPHO’s 2027 Conference “Call for Workshops” webpage, which asks presentation submitters to “seek speakers from a diverse group of faculty,” considering factors such as “gender” and “race/ethnicity.” Further, the webpage offered the highly ideological session “Hematology Consults in Transgender Medicine” as an example of a “previously accepted, well-received proposal.” Sadly, as we commented, this submission was “more concerned with ‘appropriate terminology’ than with preventing harm to gender-dysphoric children and adolescents in the first place.” We are glad to note that it has been removed from ASPHO’s website.

This example, however, does not come in isolation. Much in the way of DEI remains at ASPHO. For example, we note ASPHO’s 2025 Annual Report, with its “DEI in Action” section and membership snapshot by race/ethnicity. We see the DEI Special Interest Group hosted by ASPHO, with its call to “increasing diversity and inclusiveness … in the membership and leadership of ASPHO.” In response to a question about diversity and its role in the selection of board members, ASPHO states, “Diversity is a key value in ASPHO’s Leadership Development work.” Additionally, the 2021 ASPHO Diversity Statement highlights “programming focusing on diversity, equity, and inclusion.”

As noted on ASPHO’s own DEI webpage, DEI has become “infused” into your association. Even a disease such as sickle cell anemia is now a “topic on DEI,” according to ASPHO. Framing a medical condition in this manner needlessly politicizes a hematologic disorder, which shouldn’t need any relation to DEI to be pertinent to an organization like yours. Furthermore, DEI resources offered on the webpage include the “implicit association test,” which has poor reliability and poor predictive validity. Also included as a resource on the webpage is this article, “The time is now: Student-driven implementation of social justice and anti-racism focused curricula in medical scientist training program education,” which perpetuates the notion of systemic racism within the profession and pushes political activism directly into medical education as its solution.

One is left to wonder, are these truly the positions to which ASPHO continues to adhere? Will submissions to the 2027 ASPHO Conference be evaluated based on “how the session or speakers address ASPHO’s core values of diversity, equity, inclusion, and health equity?” Does ASPHO continue to run the DEI Special Interest Group, and for what purpose? What role will diversity play in the selection of candidates to fill the two vacancies on the 2027–2028 Board of Trustees? Is ASPHO planning on updating or removing its 2021 Diversity Statement? Does ASPHO think sickle cell disease is a DEI topic or a general patient issue? Why does ASPHO promote the discredited implicit association test? Does ASPHO believe physician-scientists need a supplemental curriculum on anti-racism?

I imagine you might be as concerned as we are that ASPHO has radically drifted from its core mission and has unfortunately subjected itself to the political whims of the day, all coming at an opportunity cost to science and clinical care. Fortunately, your role in leadership provides you with the ability to move the organization towards the vision it espouses: “improved health and a better future for children, adolescents, and young adults with cancer and blood disorders.”

We welcome your thoughtful consideration of the questions we have outlined above, as well as of the role excellence, as opposed to identity politics, should play at ASPHO. We trust you will agree that such ideological initiatives within medical associations must cease if we are to rebuild the confidence and trust of members and, even more critically, the public. As president of ASPHO, you are uniquely positioned to effect meaningful change, and we hope you will choose to do so. Certainly, there is no time like the present to end the misguided ideological adventures that have recently shaped ASPHO’s direction in ways that warrant serious concern. It is more urgent than ever to restore excellence and merit in medicine. We welcome your response and your leadership in doing so.

Sincerely,

Kurt Miceli

Chief Medical Officer, Do No Harm

[Editor’s note: To view the fully formatted letter, with footnotes, please click here.]

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2735245443-scaled.jpg 1440 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-19 08:00:362026-11-18 12:23:48Open Letter to Daniel Wechsler, MD, PhD, President of the American Society of Pediatric Hematology/Oncology
img_16542

A Medical Journal’s Unfalsifiable ‘Gender’ Contentions Are Not Science

COMMENTARY Gender Ideology Medical Journal Commentary Do No Harm Staff

Karl Popper is rolling over in his grave. The father of “falsifiability” — the notion that a properly scientific contention must be at least theoretically disprovable — would simply not believe a recent “comment” in Child and Adolescent Psychiatry and Mental Health.

That article, Jamie D. Agapoff et al.’s “Gender-affirming psychiatry: a minority stress and phenomenological framework for child and adolescent mental health,” argues that delaying children’s access to so-called gender-affirming care “should not be regarded as a neutral approach.”

Rather, “[f]rom a phenomenological perspective, psychiatric care begins by taking patients’ lived experiences seriously, regardless of age.”

But what of critics’ recognition that most children who meet the criteria for gender dysphoria will eventually desist in those feelings — that their “lived experiences” are likely temporary and thus no basis for harmful and irreparable medical interventions?

Agapoff et al. attempt to cloud that reality: “What we have come to know as ‘desistance’ is best understood as the impact of social pressure rather than a true loss of gender identity.”

Moreover, “[d]esistance, like concealment, may be better understood as an adaptive response in some to adverse social conditions, rather than evidence against the stability of transgender identities.”

The reader will note the authors’ attempt to smuggle in a double standard. Children who plead that their “gender identity” and biological sex fail to align must be “tak[en] … seriously” at any age.

Yet children who profess to no longer feel that way are simply bowing to the pressures of a “transphobic” world.

The latter is the very definition of unfalsifiability. You say one thing, your psychiatrist argues that you’ve been manipulated, and there the matter stands. A patient’s belief about the origin of his own opinions may be subject to ideological nitpicking, but it is not measurable or disprovable by science.

Attempts to do so are, in a word, unfalsifiable.

Agapoff et al.’s defense of their claim is riddled with other errors in logic.

The authors write, for example, that “[m]ore recent longitudinal studies show that when gender-diverse youth are supported, rates of persistence are high.”

But that assertion ignores the role of parental and physician “support” in encouraging gender-dysphoric kids to persist. As Kenneth J. Zucker pointed out in “The myth of persistence,” “parents who support, implement, or encourage a gender social transition (and clinicians who recommend one) are implementing a psychosocial treatment that will increase the odds of long-term persistence.”

Encouraging a child to say something, in other words, increases the chances that he will do so.

Elsewhere in their “comment,” Agapoff et al. play many of the old hits, arguing, for instance, that “current recommendations from major professional organizations consistently support individualized, developmentally appropriate gender-affirming care delivered within comprehensive multidisciplinary assessment” (emphasis added).

What about the Cass Review? What about the American Society of Plastic Surgeons?

They refer to “[g]ender affirming psychiatry as an emerging evidence-based practice” but include compromised evidence — or none.

Yet the article’s greatest flaw remains the one that would get Sir Popper riled up were he around today. The claim that desistence from gender dysphoria is mostly impossible may be pleasing to ideologues of a certain stripe, but it isn’t science.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2695718929-scaled.jpg 1706 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-18 13:54:582026-11-18 13:54:58A Medical Journal’s Unfalsifiable ‘Gender’ Contentions Are Not Science
img_941

Do No Harm Statement on Supreme Court Declining to Hear Challenge Against California’s Implicit-Bias Mandate

COMMENTARY California DEI Federal government Press Release Judicial Do No Harm Staff

SALT LAKE CITY, UT; November 17, 2026 — Yesterday, the Supreme Court of the United States (SCOTUS) declined to take up Do No Harm’s and Dr. Azadeh Khatibi’s challenge to California’s mandate that Continuing Medical Education (CME) courses contain implicit-bias curricula for physicians. Justices Gorsuch, Thomas, and Alito would have granted certiorari in the case. The Pacific Legal Foundation represented Do No Harm and Dr. Khatibi.

“Medical professionals should not be compelled by the government to participate in evidence-free implicit-bias trainings,” said Kristina Rasmussen, executive director of Do No Harm. “It is disappointing the Supreme Court declined to take up our case, but we remain encouraged that some Justices acknowledged the importance of the First Amendment issues at stake — issues that will undoubtedly continue to surface in courts across the country. We will keep fighting for constitutionally protected free speech to ensure that healthcare providers are never conscripted to deliver the government’s message. Do No Harm remains committed to finding and pursuing every avenue to eradicate political influence in the medical field.”

Three Justices expressed they would have granted certiorari. And Justice Clarence Thomas, joined by Justice Samuel Alito, dissented from the denial, writing, “California’s attempt to require private individuals in pri­vately accredited CME courses to run implicit-bias training is an evident attempt to regulate private expression.” “First Amendment protections do not give way simply because a State heavily regulates speech.”

In 2023, Do No Harm, joined by Dr. Khatibi, filed a lawsuit arguing that California’s implicit-bias training mandate violates the First Amendment speech rights of CME instructors. The district court dismissed the complaint, and the Ninth Circuit upheld that decision, claiming CME courses constitute government speech — even though the State does not create, review, or edit the content of CME courses.

The denial follows Do No Harm’s April 2026 request to SCOTUS to decide whether a state may compel private professionals to convey a contested ideological message as a condition of teaching courses required for a professional license.

See Do No Harm’s cert petition here.

See Do No Harm’s case page here.

See Justice Thomas’s dissent here.

More Details:

  • California requires physicians to complete 50 hours of CME every two years to maintain their medical licenses.
  • Courses that omit the mandated content are ineligible for CME credit, and instructors who refuse to teach it face professional consequences, such as loss of business, reputational harm, and barriers to future teaching opportunities.
  • Both Dr. Khatibi, a board-certified ophthalmologist, and members of Do No Harm create and deliver their own original CME content.

Do No Harm, established in April 2022, has rapidly gained recognition and made significant strides in its mission to safeguard healthcare from ideological threats. It has over 50,000 members, including doctors, nurses, physicians, and concerned citizens across all 50 states and 26 countries.

https://donoharmmedicine.org/wp-content/uploads/2022/11/DNH_ContentCards_PressRelease.png 675 1200 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-17 15:19:592026-11-17 15:19:59Do No Harm Statement on Supreme Court Declining to Hear Challenge Against California’s Implicit-Bias Mandate
img_16490

Will Social Workers Let the Social-Work Accreditor Tone Down Its Wokeness?

COMMENTARY DEI accrediting organization Commentary Do No Harm Staff

What happens when an academic accreditor’s members are even more ideologically radical than the organization itself? The Council on Social Work Education (CSWE) seems to be in the process of finding out.

CSWE’s foibles have been in the news before, of course, not least in our own pages.

In October 2025, we took the national association representing social-work education to task for its DEI-infused accreditation standards, the still-active 2022 version of which requires accredited programs to ensure that their students “Engage Anti-Racism, Diversity, Equity, and Inclusion (ADEI) in Practice” (Competency 3).

Accredited social-work programs must also abide by “Educational Policy 2.0: Anti-Racism, Diversity, Equity, and Inclusion (ADEI),” which requires them to “integrate anti-racism, diversity, equity, and inclusion (ADEI) approaches across the curriculum.”

We asked CSWE to ditch their DEI standards in a May 2026 open letter. The organization declined.

Yet the narrative has since taken an unexpected turn. The forthcoming 2029 accreditation standards, currently in draft form, do indeed back away from some of the 2022 version’s worst woke excesses.

The question is whether CSWE’s members will allow that much-needed reform.

A recent Wall Street Journal op-ed by Do No Harm member Pamela Garfield-Jaeger hinted at this tension, with the author writing that

[t]he council proposed new accreditation standards with less blatantly political language this year, but after sharp criticism from members, its leadership all but promised to prepare an amended draft with “more explicit language around addressing and combating racism” and “environmental justice.”

A look at the specifics is instructive.

The new Competency 3 proposed in the 2029 draft standards asks programs to ensure that social-work students “Apply Person-in-Environment Perspective in Practice,” a significantly less politically charged requirement than what currently obtains.

Educational Policy 2.0, meanwhile, has been reborn in the 2029 draft standards under the comparatively anodyne heading “Social Work Perspective.” Though programs are reminded that “[t]he social work perspective is grounded in … the purpose and values of the profession,” explicit calls to imbue curricula with DEI “approaches” have disappeared.

As hinted above, these proposed changes have not sat well with a number of social workers.

The National Collaborative for Reproductive Justice, Innovation, and Political Education in Social Work (NCRJI-SW), a left-leaning organization that engages directly with CSWE, complained in a flyer that the proposed changes “are not simply about words [but] raise fundamental questions about what we teach, what we value, and what social workers will be required to understand and challenge.”

(The group also organized a walkout at CSWE’s recent annual conference in Atlanta.)

Last week, NCRJI-SW sent an open letter to CSWE demanding that the organization “[r]estore Competency 3 as a standalone ADEI competency,” among other woke-language reinstatements. As of this writing, the letter has 1,459 cosigners.

Do No Harm recently spoke to an attendee of CSWE’s virtual Public Information Session on the proposed 2029 standards, who described that Nov. 13 meeting to us on the condition of anonymity.

In our source’s opinion, CSWE is “immovably committed” to anti-racism and DEI.

Asked during the meeting’s Q&A whether removing DEI language means that CSWE has abandoned the core values of social work, a CSWE representative assured listeners that changes in “ADEI language should not be interpreted as a departure from our values or a diminished commitment to social-work programs and the profession.” Rather, “[i]t reflects an effort to navigate an increasingly complex landscape while preserving the integrity and foundational principles of social-work education.”

Moreover, “the core principles and values of social-work education have not changed from the 2022 [standards] to the 2029 [standards] draft. […] Programs will continue to be expected to uphold the values while maintaining that flexibility to determine how they are taught based on their institution and legislative context.”

If that’s the case, then why bother altering Competency 3 and other woke requirements in the first place? As passed along by our source, CSWE’s answer to a question in that vein was that “the current political and higher-education landscape” demands it.

That answer gives us serious pause. CSWE may indeed stand up to the most ideological voices in the social-work community, at least on paper.

But it isn’t at all clear that they really mean it.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2747679179-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-17 10:19:412026-11-17 10:19:41Will Social Workers Let the Social-Work Accreditor Tone Down Its Wokeness?
img_941

Do No Harm and the American College of Pediatricians Urge the ACGME Review Committee for Pediatrics to Allow Resident Physicians to Opt Out of Sex-Rejecting Interventions

COMMENTARY Gender Ideology Accreditation Council for Graduate Medical Education accrediting organization Press Release Do No Harm Staff

Salt Lake City, UT: November 17, 2026 – Today, Do No Harm (DNH) and the American College of Pediatricians (ACPeds) sent a letter calling on the Accreditation Council for Graduate Medical Education (ACGME) Review Committee for Pediatrics to revise its program requirements to allow residents to opt out of participating in sex-rejecting interventions for reasons of conscience.

The ACGME’s current Program Requirements for Pediatrics do not address situations in which a resident physician may hold sincere moral or religious objections to direct participation in sex-rejecting interventions. DNH and ACPeds have now submitted ready-to-use language to provide clear guidelines for accommodating residents in such situations.

“Resident physicians in pediatric training programs should be able to opt out of direct involvement with sex-rejecting interventions that violate their sincerely held moral, ethical, or religious beliefs,” said Dr. Kurt Miceli, chief medical officer at Do No Harm. “Our proposed language would permit pediatric residents to decline participation in these harmful procedures while preserving program-level training requirements and patient-care obligations. The ACGME’s Review Committee for Pediatrics should recognize the serious concerns held by many residents amid the changing landscape of gender treatment and allow for the necessary protections to be put in place.”

“The American College of Pediatricians is proud to join Do No Harm in calling on the ACGME to establish clear conscience protections for pediatric residents,” said Dr. Michael Artigues, president of ACPeds. “No resident should be forced to choose between participating in harmful sex-rejecting interventions and completing their medical education. As the evidence base on sex-rejecting interventions in minors continues to evolve, and as leading international organizations reassess and move back from these practices, it is more important than ever that residency programs have clear, standardized guidance for accommodating conscientious objection. Residents should never be forced to participate in sex-rejecting interventions that violate their conscience or the standards of good medicine.”

DNH and ACPeds’ letter notes that the proposed opt-out language is modeled after the ACGME’s induced-abortion guidelines established by the Review Committee for Obstetrics and Gynecology. The groups argue that introducing an opt-out for sex-rejecting interventions would create a consistent framework across pediatric residency programs that would reduce ambiguity while preserving patient safety, continuity of care, and educational requirements.

More details:

  • DNH and ACPeds highlight that the ACGME’s formal opt-out policy for specific procedures in obstetrics and gynecology residency training does not compromise the clinical or educational integrity of that training.
  • The proposed language is intentionally limited to conscientious objection to direct participation in sex-rejecting interventions and does not establish a general right to decline other components of pediatric training or care.
  • The policy does not permit avoidance of broader professional responsibilities and explicitly requires that any such declinations must not compromise patient safety, continuity of care, or timely access to treatment.

Click here to read the letter and the proposed language.


Do No Harm, established in April 2022, has rapidly gained recognition and made significant strides in its mission to safeguard healthcare from ideological threats. It has over 50,000 members, including doctors, nurses, physicians, and concerned citizens across all 50 states and 26 countries.

The American College of Pediatricians is a medical membership organization of pediatricians and healthcare professionals who care for children across 47 states and 5 countries. We promote the optimal health and well-being of all children through evidence-based medicine. For more information, please visit our website at www.acpeds.org.

https://donoharmmedicine.org/wp-content/uploads/2022/11/DNH_ContentCards_PressRelease.png 675 1200 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-17 10:14:532026-11-17 10:14:53Do No Harm and the American College of Pediatricians Urge the ACGME Review Committee for Pediatrics to Allow Resident Physicians to Opt Out of Sex-Rejecting Interventions
img_16484

Does the Pennsylvania Medical Society Speak For Doctors?

COMMENTARY Pennsylvania DEI Medical association Commentary Kurt Miceli, MD

Is election season leaving you sick to your stomach? Pennsylvanians may be even more nauseated to learn what’s happening at one of our state’s most important medical institutions.

The Pennsylvania Medical Society held its annual meeting in Hershey over the weekend. Surprisingly, the organization that represents the Commonwealth’s doctors chose mediocrity over excellence and ideology over evidence when it comes to medical education. That should worry every Pennsylvanian, since all of us depend on excellent medical care.

As a psychiatrist, I’ve been a member of the society for 15 years, and I attended this year’s meeting as a delegate. I also work at a medical organization that advocates for the highest standards of physician training and patient care. As such, I submitted several resolutions for my fellow physicians to consider, in the hopes of reaffirming our state’s commitment to equal and excellent medical care.

My first resolution was simple: I urged the Pennsylvania Medical Society to support stronger standards in the national medical licensing exam. The exam is taken in three stages, known as “steps,” that aspiring physicians must pass to obtain a medical license. Yet in 2022, the first step dropped numeric scoring in favor of a pass/fail system.

The reason is disturbing: Political activists have long opposed numeric scoring on the grounds of “equity.” Specifically, they dislike that white and Asian students tend to get higher grades, on average, than black and Hispanic students. Ditching the grades helps cover that up. As national medical organizations have argued, the change helps “minimize racial demographic differences.”

But hiding reality is dangerous — for patients. Without grades, residency programs struggle to tell which medical students are the most likely to become the best physicians. Students themselves also have less reason to excel, because there’s little benefit to studying harder. That doesn’t bode well for patients, who need every physician to strive for excellence, not just “good enough.”

Unfortunately, the delegates to the Pennsylvania Medical Society meeting saw no problem encouraging mediocrity. They ultimately voted down my resolution 153 to 26.

I also offered a resolution opposing the politicization of continuing medical education. Many states — including our neighbors in Maryland and New Jersey — require many medical professionals to get training in things like “implicit bias” and “structural racism” as a condition of maintaining their license. Yet the science behind these trainings is shaky, at best, and telling patients their doctors can’t be trusted to treat them fairly risks real harm to the doctor-patient relationship.

The overriding message of this training is that doctors often mistreat patients with different skin colors. That’s an insult to physicians and a direct threat to patient trust in healthcare, which is low enough already. Besides, when doctors have to spend time learning about their own “bias” and “systems of oppression,” they aren’t spending time learning about the latest clinical skills and treatment strategies. Continuing medical education should promote better healthcare, not activist talking points. It should be based on scientific rigor, and as a medical society we should be proud to say that.

Sadly, my second resolution failed, as well. Only 66 of the delegates in attendance voted in favor, while 113 voted against it.

But do the delegates who voted against my resolutions really speak for Pennsylvania’s physicians? Many were medical students, not physicians, and overall there were less than 200 delegates actively participating — a fraction of the state’s 49,000 active doctors. Most physicians I know steer clear of the organization because they don’t see its value or oppose its politicization. But the Pennsylvania Medical Society still purports to be “the voice” of all the state’s doctors. In reality, it speaks for a small, self-selected slice of the profession — and its votes shouldn’t be mistaken for the views of Pennsylvania’s physicians.

In my experience, doctors want what patients deserve: a world-class medical system that trains excellent physicians and provides excellent care. It pains me that my own state medical society is fighting against this noble and necessary goal. But until more doctors get involved — and I hope they do — the Pennsylvania Medical Society will suffer from the same sickening politicization that defines the current election season.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_722835706-1-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-16 14:26:412026-11-16 14:26:41Does the Pennsylvania Medical Society Speak For Doctors?
img_16477

On Hormone Therapy ‘Satisfaction,’ Caution Is Advised

COMMENTARY Gender Ideology Medical Journal Commentary Kurt Miceli, MD

[Editor’s note: This piece originally appeared as a comment in response to Laura Kuper et al.’s “Satisfaction, Regret, and Harm After Hormone Therapy in Youth From a Multidisciplinary Gender Clinic” in JAMA Pediatrics. That article is available here.]

Based on this study one might conclude that satisfaction & lack of regret are paramount to evaluating care of youth with gender dysphoria. The authors claim their results “support … the existing standards of care” & “do not support efforts to … ban access” to cross-sex hormones for minors. That conclusion goes beyond what the data can establish.

First, patient satisfaction measures must be taken with caution. Relevant to all of medicine is Joshua Fenton et al.’s work showing that “higher patient satisfaction was associated with … greater inpatient use, higher overall health care … expenditures, and increased mortality.” Further, Brian Sites et al. conclude that “[a]mong patients with musculoskeletal conditions, those using prescription opioids are more likely to be highly satisfied with their care.” And Kathryn Martinez et al. find that “patients who receive antibiotics for [respiratory tract infections] are more satisfied.”

Simply, satisfaction doesn’t necessarily equal appropriate care.

Read the full piece in JAMA Pediatrics.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2514636311-scaled.jpg 1788 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-16 10:42:182026-11-16 10:42:18On Hormone Therapy ‘Satisfaction,’ Caution Is Advised
img_16462

SUNY Downstate’s Regrettable ‘Indigenous’-Medicine Partnership

COMMENTARY New York DEI SUNY Downstate Health Sciences University College of Medicine Public university Commentary Do No Harm Staff

A comically woke activist foundation counts among its “partners” a public health-sciences university with more than 2,000 enrollees. What are our future doctors, nurses, and public-health officials learning these days?

If the ARIAH Foundation’s website is any guide, the answer to that question is not encouraging. Standing for the Advancement of Reproductive Innovation through Artistry and Healing, ARIAH “is dedicated to improving the mental and physical health of Black, Indigenous, and People of Color (BIPOC), particularly birthing people” — not women — “through advocacy, education, and healing practices.”

The Foundation’s “goal is to mitigate the lasting impact of systemic racism and oppression on the sexual, reproductive health and birth outcomes within underserved communities.”

To these ideological clichés, ARIAH adds a dash of outright quackery. Among the projects produced by the Foundation’s “global partnership[s]” is an Indonesia-based “maternal health initiative” focused in part on “indigenous midwifery.”

Clicking “Learn More” beneath that program description takes one to the website of the Bumi Sehat Foundation International, an American 501(c)(3) nonprofit that works with ARIAH on the Indonesia initiative.

Further exploration of that site reveals that “[b]abies are sung earthside by midwives and families,” a practice that presumably illustrates what ARIAH means when it promises “culturally rooted approaches to maternal wellness.”

There is nothing inherently wrong with delivering babies in a way that honors the mother’s beliefs. The problem comes when “indigenous” notions crowd out medical science–based best practices, a concern one can’t help having upon closer examination of both the Bumi Sehat and ARIAH websites.

Bumi Sehat writes, for example, that “[w]omen deserve kind and gentle care.” We agree and expect as much from obstetricians of all backgrounds.

However, the organization also states, on the same page, that “[g]entle birth by nature has fewer ‘man made complications’[;] thus women and their babies are healthier and leave our clinic with their hearts intact” (emphasis added).

This is, to say the least, a perspective that neglects the advances of clinical medicine. Furthermore, one needn’t stretch one’s imagination excessively to envision a scenario in which concern for a patient’s metaphysical “heart” supplants concern for her literal one.

Back on the ARIAH website, one recently plugged event cohosted by the Foundation, the Mother Wit 2026 Series, promises “ancient wisdom” in the form of “holistic healing,” “ancient practices,” and “indigenous technology.”

Our concerns are the same here. If those elements accompany but remain secondary to fetal-monitoring devices and IV infusion pumps, then perhaps they will do some emotional good. If they take the place of scientific medicine, then they very well may do great harm.

We might dismiss all of this as a lamentable curiosity were it not for ARIAH’s advertised partnership with SUNY Downstate Health Sciences University, an institution ostensibly dedicated to “provid[ing] outstanding education [to future] physicians, scientists, nurses and other healthcare professionals” and to “advanc[ing] knowledge through cutting edge research and translat[ing] it into practice.”

Those pledges sit uneasily alongside, say, SUNY Downstate’s hosting of one of the previous year’s Mother Wit events (“The Future of Birthing Is Now”) and its boast that the ARIAH Foundation is one of its “community partners.”

The business of a health-sciences university is first and foremost to teach the health sciences, not “the healing traditions of Indigenous peoples,” however historically or spiritually relevant they may be.

If the ARIAH Foundation and its ilk are going to exist, SUNY Downstate should have nothing to do with them.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2271796465-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-12 15:26:272026-11-12 15:26:27SUNY Downstate’s Regrettable ‘Indigenous’-Medicine Partnership
img_16435

In British Columbia, a Warning on ‘Transing Kids’

COMMENTARY Canada Gender Ideology Commentary Do No Harm Staff

Good neighbors warn one another when something is awry. Perhaps without meaning to, a Canadian province’s official pediatric transgender apparatus provides a warning to American readers about where “gender” ideologues will take this country if not opposed.

The official site in question, Trans Care BC, is a “provincial clinical program” operated by the publicly funded Provincial Health Services Authority (PHSA) in British Columbia.

Though many of Trans Care BC’s services seem designed for adults, an entire page on the program’s website is explicitly pitched to “Youth.”

On this page, one learns that “[c]onnecting with other trans, Two-Spirit[,] and non-binary youth can be a wonderful way to make friends, talk about issues that are important to you[,] and learn from others who may be going through similar experiences.”

One reads about Queer Straight Alliances (QSAs), groups that focus in part “on support, raising awareness about the issues faced by … trans people, and challenging discrimination based on gender identity.”

In a “Peer Support Directory” linked to on the page, “children” are invited to “[f]ind peer support groups and services.” Among the groups listed if one clicks the “Children & youth” audience button are

  • The Foundry 2SLGBTQIA+ group in Campbell River, which offers “a program by appointment that provides gender-affirming gear, such as chest binders and breast forms”;
  • Chilliwack Rainbow Families, which provides “educational and peer support to children and parents of children under 12 experiencing gender diversity” and encourages participants to “bring an open mind”;
  • The Fraser Youth Society, offering “2SLGBTQIA+ and Allied Youth (ages 13 – 19) … gender-affirming wear”; and
  • Friends of Dorothy, in Langley, in which “youth ages 12 to 24” — that is not a typo — “safely explore identity, connect with[,] and [are] supported by peers.”

If anything, matters are even worse back on the homepage, where scrolling down produces options for “Supporting children under 12” and “Supporting youth 13–18.”

Horrifyingly, clicking on the former brings up options for “Affirmation & social transition” (bad enough) and “Medical options” (the stuff of nightmares).

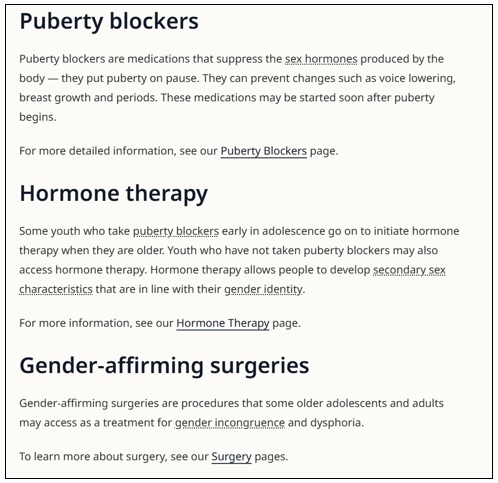
The second of those pages introduces site visitors to puberty blockers (“These medications may be started soon after puberty begins”), hormone therapy (“Some youth who take puberty blockers early in adolescence go on to initiate hormone therapy when they are older”), and so-called gender-affirming surgeries (“Gender-affirming surgeries are procedures that some older adolescents and adults may access”).

Like several other pages on the Trans Care BC website, an eye-catching banner offers those who “need support” the option to “[c]ontact our team of experienced health navigators for information about gender-affirming care in B.C.”

All of this is paid for by regular Canadians. Indeed, the site shocks the conscience in part because it is so user-friendly, well-designed, thorough, and official — in a word, costly. Someone put together Trans Care BC’s website with attention to detail and a big enough budget to facilitate that careful work.

Let us have no doubts: That person has ideological allies on this side of the border. Some American states already point residents to “gender-affirming care” online, just not yet with British Columbia’s slick and seductive polish. Those allies would happily close the gap.

We can’t say we weren’t warned if we let them.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2447458311-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-10 08:44:242026-11-10 08:44:24In British Columbia, a Warning on ‘Transing Kids’
img_16398

The Lancet Does Politics Again

COMMENTARY Europe DEI Medical Journal Commentary Do No Harm Staff

When medical journals waste their time chasing ideological rainbows, they undermine the authority of physicians and the scientific basis of medical practice. That is as true in Britain as it is here.

Case in point: The Lancet, founded in 1823 by the English surgeon Thomas Wakley. Recent (and not so recent) articles in that august publication have forsaken the journal’s pledge to provide “[t]he best science for better lives” and have delivered instead run-of-the-mill progressive orthodoxies.

Among the lowlights:

  • “An open letter for the people in Gaza,” published in 2014 and notable for its suggestion that Israeli operations in Hamas-held territory had resulted in a “war crime” and a “massacre”;
  • “Reviving the US CDC,” a 2020 editorial explicitly calling for Americans to vote President Trump out of office;
  • “Offline: Extinction or rebellion?,” a 2019 comment praising the radical climate-change group Extinction Rebellion.

We could go on but won’t. Suffice it to say that the journal’s interest in wading into political waters has not diminished.

No other conclusion is possible when one examines “A guide to anti-racist medicine,” Dr. Sruthi Saravanan’s October 24, 2026, review of the edited collection Anti-Racist Medicine: An Essential Guide to Advancing Equity in Medical Education, Research, Technology, Policy, and Practice.

That volume, edited by Zeshan Qureshi (a physician) and Mehrunisha Suleman (a “medically trained bioethicist”), bills itself as a “first-of-its-kind textbook address[ing] increasingly important questions associated with race, ethnicity, and medicine.”

Needless to say, Saravanan’s review is overwhelmingly positive.

To begin with, Saravanan sets forth the highly ideological contention that “[f]ar-right movements in many countries are fuelling xenophobia and racism and gaining traction through policy and media.”

It is “in this context,” the author continues, that the “timely” book under consideration “challenges the racist narratives and misconceptions that have been instilled in medicine.”

What are those racist narratives and misconceptions, exactly? Though Saravanan’s review is curiously short on specifics, one particular complaint does emerge — that “physicians and researchers must be,” and presumably have not been, “careful in how we define and describe racism in our scholarly efforts and clinical practice, as [racism] continues to be a determinant of health equity within minority communities.”

Note the circular reasoning thus employed. Doctors must “define” racism carefully because racism affects the health of “minority communities.” Yet how do we know that racism does that grim work until we define it? Moreover, do we have any reason to believe that insufficiently expansive definitions of racism will be accepted?

This is but one moment in Saravanan’s piece in which ideological assumptions get ahead of the evidence. Elsewhere, the author joins the book itself in calling for medical practitioners and researchers to bring an “intersectional perspective [to their work] to ensure equity is achieved.”

He suggests that “[c]linicians’ own racial biases and presumptions about people can be harmful, affecting diagnostic judgement and outcomes for patients.”

He argues that “[a]ntiracism should underpin admission processes, medical school curricula, and postgraduate training, as racial biases and prejudice can lead to differential attainment.”

He insists that “institutional racism persists in health-care systems.”

No proof of these claims makes its way into the article. Indeed, the thoughtful reader is likely to experience the piece not as an argument but as a dashed-off list of progressive medical talking points.

Perhaps most damagingly, the article repeats the book’s call for the further politicization of medical scholarship, approvingly informing us that “[t]he authors also call for medical journal editors to uphold the diverse scholarship that is necessary to advance scientific knowledge and promote equitable health care.”

In fact, accurate, evidence-based, replicable scholarship will advance scientific knowledge and promote better health outcomes for patients of all races. Whether that scholarship is “diverse” matters not.

Saravanan concludes by remarking that “Anti-Racist Medicine provides the blueprint for creating a more equitable health-care system.”

Whether or not that’s true, keeping politicized book reviews out of medical journals is certainly part of the blueprint for rescuing medicine from ideological capture.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_1686925927-1-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-05 13:22:522026-11-05 13:22:52The Lancet Does Politics Again
img_500

Do No Harm Files IRS Comment on Private-School Nondiscrimination

COMMENTARY DEI Federal government, Private university Commentary Executive Do No Harm Staff

Earlier this week, Do No Harm submitted an official comment to the IRS on the proposed rule “Racial Nondiscrimination in Private Schools.”

We strongly support this codification of the longstanding requirement that a private school must maintain a racially nondiscriminatory policy in order to qualify for tax exemption.

Our reasons for submitting the comment are these. First, we explain why a school’s asserted good intentions should not excuse race-based discrimination. A student denied an educational opportunity because of his or her race or the race of other applicants suffers the same injury regardless of whether the school calls its discriminatory policy “benign” or “remedial.”

Second, we write in support of applying this principle to private schools claiming tax exemption. A school engaging in racial discrimination should not be able to preserve federal tax benefits (in the form of tax-exempt status) simply because it does not receive federal financial assistance in the form of actual payments.

Finally, we recommend that the IRS guard against the use of facially neutral criteria as disguised racial preferences. The Supreme Court addressed that danger directly in Students for Fair Admissions v. Harvard: Universities may not use application essays or other means to recreate the admissions regime the Court held unlawful. A student’s experience may be considered for what it reveals about that individual’s qualities — not as a device for awarding a preference based on race.

Do No Harm commends the Treasury Department and the IRS for a rule that equips the government to flag and eliminate racial discrimination in private education, regardless of the purpose offered to justify it.

Please read our full comment here or below.

DNH Comment supporting IRS Racial Nondiscrimination in Private Schools NPRM
https://donoharmmedicine.org/wp-content/uploads/2022/06/DNH_ContentCards_OfficialComment.png 675 1200 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-05 10:11:072026-11-05 10:11:07Do No Harm Files IRS Comment on Private-School Nondiscrimination
img_500

Do No Harm Files HRSA Comment on Children’s Teaching Hospitals and Sex-Rejecting Procedures

COMMENTARY Gender Ideology Hospital System Commentary Executive Do No Harm Staff

Earlier today, Do No Harm submitted an official comment in support of a Health Resources and Services Administration (HRSA) proposal that would help the government track the extent to which it is funding pediatric sex-rejecting ideology.

Though complicated, the proposed change deserves the backing of all who wish to protect children from damaging and unproven medical interventions.

The Children’s Hospitals Graduate Medical Education (CHGME) Payment Program exists to provide federal funding to freestanding children’s teaching hospitals.

Such institutions usually treat fewer Medicare patients than do general teaching hospitals and consequently received less federal support until the creation of the CHGME Payment Program in 1999.

By statute, institutional grant recipients of CHGME Payment Program funding must provide annual data about their operations to the federal government. HRSA’s new proposal would add to the required data collection an additional dropdown option for three questions.

Specifically, the revised data-collection instrument would

  • add “Sex Rejecting Procedures and Services for Minors” as a dropdown option on the Program Curriculum Changes form;
  • add “Individuals Receiving Training on Sex Rejecting Procedures and Services for Minors” as a dropdown option on the Individual Characteristics form; and
  • add “This Site Offers Sex Rejecting Procedures and Services for Minors” as a dropdown option on the Experiential Training Sites form.

In short, the government would gain a clearer sense of how taxpayer money is being used to train physicians in pediatric “gender-affirming care.”

HRSA asks public commenters to address “the necessity and utility of the proposed information collection for the proper performance of the agency’s functions.”

The proposal meets that standard for three reasons.

First, sex-rejecting procedures have been performed on minors at scale in the very hospitals the CHGME Payment Program funds. A Do No Harm analysis of the period 2019–2023 identified 12 hospitals as the worst-offending children’s hospitals promoting sex-rejecting procedures to minors. Every one of those 12 children’s hospitals was a CHGME Payment Program grantee.

Second, the federal government has no reliable means of collecting this information at present, and this collection supplies one, thus allowing policymakers responsible for a training program of more than $370 million a year to know whether the program is preparing physicians to deliver interventions with “very uncertain” benefits and substantial evidence of harm.

Third, given the current state of the evidence, whether a federally funded training program teaches these procedures speaks directly to the quality of the education the program provides. Training residents and fellows to deliver interventions with “very uncertain” benefits and “less uncertain” harms is not high-quality graduate medical education.

We urge our members to file comments of their own, particularly (but not exclusively) if they have firsthand experience of witnessing or engaging with gender ideology at a children’s teaching hospital funded by the CHGME Payment Program and believe that ideological intrusion to be indicative of poor quality.

Public comments needn’t be formal, lengthy, or formatted in a specific way. A few sentences will do.

Please join us in telling the HRSA that the federal government should ask CHGME Payment Program grant recipients for the information described above.

Email [email protected] to make a public comment of your own. (Be sure to mention the title “Bureau of Health Workforce Performance Data Collection, OMB No. 0906-0086-Revision.”) Deadline: Nov. 9.

Or click here, or scroll down, to read Do No Harm’s full comment.

DNH-HRSA-CHGME-ICR-Comment-11-4-26
https://donoharmmedicine.org/wp-content/uploads/2022/06/DNH_ContentCards_OfficialComment.png 675 1200 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-04 14:32:462026-11-04 14:32:46Do No Harm Files HRSA Comment on Children’s Teaching Hospitals and Sex-Rejecting Procedures
img_16361

The American Academy of Family Physicians’ Radical ‘Gender’ Tradition

COMMENTARY Gender Ideology American Academy of Family Physicians Professional organization Commentary Do No Harm Staff

Chronicling pediatric “gender” radicalism at the American Academy of Family Physicians’ annual conference has become something of a fall tradition at Do No Harm.

We would just as soon break the habit if allowed.

Sadly, AAFP seems determined to politicize medicine anew each year, unapologetically departing from the evidentiary standard and throwing in their lot with vogue ideology.

In 2024, for example, one AAFP conference speaker stated falsely that “[t]here’s no question that it [pubertal suppression and cross-sex hormones] works; there’s no question that it saves lives,” ignoring the fact that the exhaustive Cass Review had recently determined that the evidence for such procedures is of “poor quality.”

A 2025 session, titled “Gender Affirming Puberty Suppression: Initiation and Management,” instructed attendees to give into a 12-year-old’s easily manipulable desires “over and against the counsel of both his parents and the mass of emerging medical evidence,” as the Washington Stand would later characterize the presentation.

This year’s conference, held October 20–24 in Nashville, continued the trend, not least in a session titled “Family Physicians’ Role in Caring for Transgender Youth,” led by Kevin S. Wang, MD.

There, Dr. Wang delivered a presentation so steeped in ideology that one questions whether a single word had scientific value.

The problems started with the Learning Objectives themselves, three propositions that took for granted the desirability of “gender-affirming medical care,” including “surgical care,” for children.

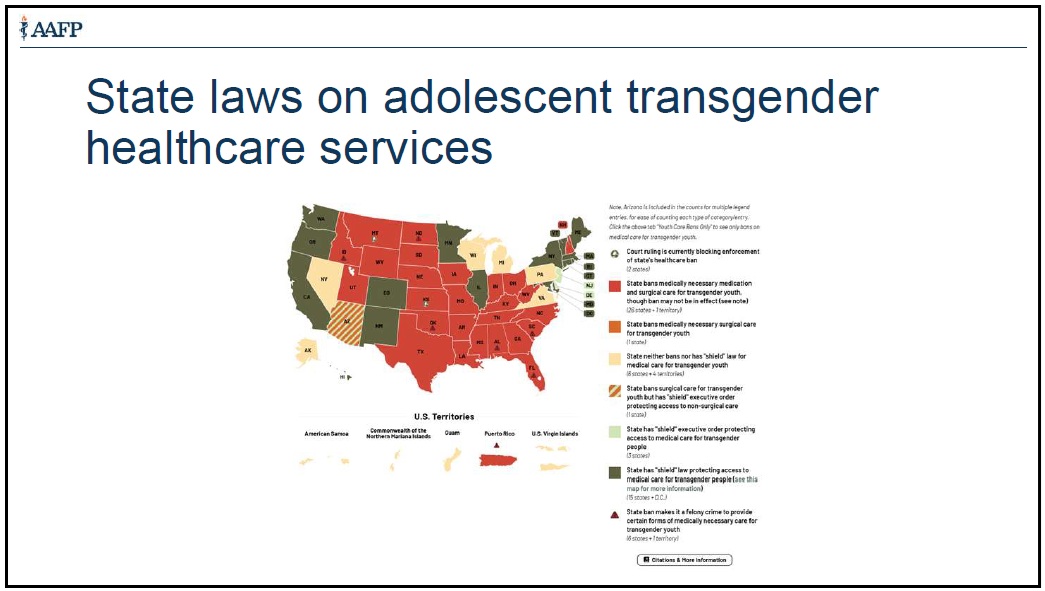
Shortly thereafter, Wang’s presentation featured a legal map dedicated to “adolescent transgender healthcare services” and composed from an explicitly ideological perspective.

(Specifically, the map revealed which states ban “medically necessary medication and surgical care for transgender youth,” a framing that begs the question whether any such “care” is, in fact, “medically necessary.”)

Things got worse later in the presentation. One slide argued falsely that “[t]ransgender healthcare is lifesaving care,” a claim clearly meant to apply to the “youths” mentioned elsewhere on the slide.

Another purported to offer a “summary of the current evidence” concerning “the provision of healthcare services to transgender and gender-diverse adolescents” but included a graphic implying that some of the so-called evidence comes from WPATH, a discredited medical “authority” currently being sued by the Federal Trade Commission for helping providers to make false and unsubstantiated claims to parents.

A grotesque slide near the presentation’s midway point concerned “[t]alking with families at visits” and presented a series of leading questions (e.g., “Do you feel more like a boy? A girl? Both? Neither?”) with which children might be inducted into pediatric transgender ideology.

Still later slides considered how best to treat “[y]ounger gender-diverse patients” less than 11 years of age, with the second slide in that sequence urging physicians and parents to “support” gender-dysphoric young children with “clothing” and “pronouns.”

The same slide promised without evidence that such actions “provid[e] significant behavioral and mental health relief and improvement.”

This is ideological radicalism, not science. It belongs at a political convention, not the flagship annual gathering of an influential medical professional organization.

As previously stated, Do No Harm would love to wake up to a world in which the AAFP can be trusted to stick to the facts, stop advocating for damaging, irreversible medical procedures, and draw the line at manipulating children.

Will 2027 be the year? We have few reasons to suspect so, but we hope for it.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_1928629448-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-11-03 11:47:112026-11-03 11:47:11The American Academy of Family Physicians’ Radical ‘Gender’ Tradition
img_16334

Judgment Day for the American Psychological Association

COMMENTARY DEI American Psychological Association Professional organization Commentary Do No Harm Staff

The bill may be coming due for unchecked antisemitism at the American Psychological Association (APA). All who oppose the politicization of scientific professional organizations should welcome that outcome.

Though the APA has long allowed political ideology to seep into its work as “the leading scientific and professional organization representing psychology in the United States,” its current trouble can be traced to a recent campaign objecting to an APA resolution on antisemitic and anti-Jewish prejudice, amended in 2007.

There, among other observations, the APA Council of Representatives noted (accurately) that “the link between extreme anti-Israel rhetoric and deeds directed against Jewish individuals and communities has become an observable global trend and has at times unleashed demonization and dehumanization of Jews.”

Put simply, criticism of the state of Israel too often provides cover for Jew-hatred of the basest kind.

This concession to reality did not sit well with Psychologists for Justice in Palestine (PJP), a “collective of psychologists, psychology students, and affiliated mental health professionals … who are in solidarity with the struggle for Palestinian Liberation.” In 2025, PJP delivered a petition to APA leadership calling for the organization to “reject the conflation of antisemitism with criticism of the nation-state of Israel and [to] recognize that this conflation is discriminatory.”

PJP’s petition made for uneasy reading. Arguing that the 2007 amended resolution had “been used to obstruct efforts to promote and protect human rights,” PJP complained of Israel’s “violence and racism toward Palestinians,” as well as the Jewish state’s “genocidal actions.”

Tellingly, the latter phrase was hyperlinked and took readers to a United Nations website featuring commentary by UN Special Rapporteur Francesca Albanese, an “expert” with her own history of antisemitic commentary.

This unhappiness on the part of an APA faction might have mattered less had that faction’s views not come to be represented at the highest level of the organization. But they did.

Among the signers of PJP’s petition was Candice Hargons, who, earlier this month, was elected the 2028 APA president. (Hargons will spend 2027 as president-elect.)

Nor is Hargons’s relationship with PJP limited to her name on a single document. Instead, PJP formally endorsed Hargons’s candidacy, a move that Hargons publicly declared herself “honored and deeply grateful to share.”

Coming several months before this exchange was the APA Council of Representatives’ February adoption of a new 2026 resolution on antisemitism, a vote celebrated by PJP.

Unlike the 2007 amended resolution, the 2026 document invokes “the weaponization of antisemitism” — defined therein as “the manipulative or bad faith invocation of accusations [of antisemitism] to silence legitimate criticism, scholarship, or activism.”

Such weaponization, the document continues, “creates significant adverse consequences for Jews and non-Jews who oppose the state of Israel’s actions and support Palestinian rights.”

Notable as well in the 2026 resolution is a “Therefore Be It Resolved” clause stating “that the American Psychological Association will conduct regular impact assessments to ensure that our antisemitism policy addresses the harms of antisemitism along with intersecting forms of oppression” (emphasis added). One might reasonably ask why a concept from Critical Race Theory has intruded into a document guiding institutional policy toward antisemitism.

By late July, the situation had worsened. As Psychologists Against Antisemitism executive board member Daniel Balva recounted in the Times of Israel, a PJP email in advance of the August 2026 APA conference urged attendees to “show solidarity by wearing a keffiyeh or ‘Palestine colors,’ [to] read a prewritten ‘Land and Genocide Acknowledgement’ before professional presentations, [and to] attend programming focused on Palestinian liberation.”

One weeps to recall that many academic psychologists attending the annual gathering may have done so on the taxpayer’s dime.

Happily, the federal government is taking steps to oppose the politicization of the nation’s largest association of psychologists. In September, a Department of Education advisory committee on accreditation recommended suspending recognition of the APA’s Commission on Accreditation over the organization’s continued failures to address antisemitism.

Just yesterday, the House Committee on Education & Workforce released “Antisemitism at the American Psychological Association,” a scathing majority staff report concluding that “radical activist-academics have successfully co-opted the APA to politicize the association and promote ideology that demonizes Israel, minimizes Hamas terrorism, and portrays Jews as white oppressors.”

Thus do Hargons and other APA leaders find themselves in an increasingly difficult position. Whereas at one time the politicization of science could be quietly effected, reformers are now watching. So is Uncle Sam.

No longer will the APA and similar organizations be automatically treated as neutral expert bodies, especially where their role in academic accreditation is concerned. That trust will have to be re-earned.

The way out of this mess is simple enough, though admittedly not easy given the apparent beliefs of the association’s incoming regime. Depoliticize, stop giving cover to antisemites, and stay out of the “Palestine” business altogether.

Hargons et al. should take that advice seriously. The APA’s continuing relevance as a representative of American psychologists may depend on it.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2468735439-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-10-30 13:21:512026-10-30 13:21:51Judgment Day for the American Psychological Association
img_16274

DSM, Not DEI

COMMENTARY DEI Medical Journal Commentary Do No Harm Staff

A series of commentaries in the May 2026 issue of the American Journal of Psychiatry plots a future “roadmap” for the Diagnostic and Statistical Manual of Mental Disorders (DSM), a new version of which is currently being planned by the American Psychiatric Association’s Future DSM Strategic Committee.

For the sake of patients of all races and ethnicities, we hope these stated plans for the future DSM are seriously reconsidered.

Our reason is that at least two of the articles approach psychiatric diagnostics from a politicized angle. Indeed, it is not too much to say that the principles of “Diversity, Equity, and Inclusion” (DEI) are among the most important philosophical — we do not say scientific — pillars holding up the proposed DSM edifice.

Take, for example, “The Future of DSM: A Strategic Vision for Incorporating Socioeconomic, Cultural, and Environmental Determinants and Intersectionality,” whose lead author, Milton L. Wainberg, MD, is chair of the Future DSM Strategic Committee’s Socioeconomic, Cultural, and Environmental Determinants of Mental Health Subcommittee.

Wainberg et al. argue that “future DSM models could embed culture and … intersectionality not only as contextual variables that modify stressors, access, and stigma, but also as central, transdiagnostic processes shaping diagnosis, treatment, and recovery.”

They propose that viewing so-called socioeconomic, cultural, and environmental determinants of health (SCE-DoH) “through an intersectional lens places emphasis on the fact that structural advantages and disadvantages do not affect everyone equally due to differential exposure to risk and access to support.”

They argue, moreover, that “[a] richer integration [of] SCE-DoH as both context and process is essential to capturing the complexity of lived experience and ensuring diagnostic equity and accuracy.”

As is often the case with bad ideas, there is a kernel of truth here. Psychiatrists should consider the extent to which their patients’ psychiatric illnesses have a cultural context. And it is certainly the case that one’s environment, real or virtual (e.g., social media), can adversely impact one’s mental health.

Nevertheless, the thinking expressed by Wainberg et al. is dangerous. Proposing that intersectionality and its perceived “systems of oppression” be treated as “central, transdiagnostic processes shaping diagnosis” risks placing ideological constructs on equal diagnostic footing with the appearance, duration, and clinical significance of actual psychiatric symptoms.

More than that: By focusing on patients’ “intersectional” identities — i.e., their presumed victimization as a result of their race and gender and disability status, religion, et cetera — psychiatrists risk reducing individual care-seekers to representatives of crass political categories.

The second commentary in question, “Initial Strategy for the Future of DSM,” offers more of the same, contending, for example, that “entrenched responses to racial characteristics … have an impact on psychiatric assessment” and that the future DSM has a goal of “integrating … socioeconomic, cultural and environmental determinants of mental health.”

As lead author María A. Oquendo, MD, PhD, chair of the overall Future DSM Strategic Committee, notes, the Dahlgren-Whitehead model of health determinants “recommends consideration of socioeconomic, cultural, and environmental determinants in clinical formulations and treatment planning.” They add that the future DSM should “integrate these determinants and intersectionality into psychiatric assessment.”

That plan isn’t a good one for patients of any race. Yes, psychiatrists must take into account the cultural contexts of mental-health disorders, as previously acknowledged, but to wed “social determinants of health” ideology to “intersectionality,” as Oquendo et al. propose, is necessarily to go beyond scientifically grounded diagnostics and treatment into the realm of political theory.

Moreover, as Do No Harm has previously explained, it is not the role of medical professionals to become activists or reformers. Such activities naturally follow from “social determinants of health” ideology and are well beyond the purview of physicians. (Again, we grant that doctors must seek to understand the context in which a particular disease presents.)

As for nonpsychiatric medicine, so for psychiatric medicine: The mission creep that occurs when psychiatrists chase the Dahlgren-Whitehead rainbow comes at the detriment of medicine’s core focus. Diagnostic accuracy and proper treatment will follow when psychiatrists examine the patients in front of them as individuals, not as representatives of intersectionally victimized classes.

If the next version of the DSM encourages that framework instead of the one described in these commentaries, it will have done very well.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2548165823-scaled.jpg 1440 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-10-28 10:42:322026-10-28 10:42:32DSM, Not DEI
img_941

Do No Harm Expands IRS Complaint Calling for Investigation into American Medical Association Foundation’s Tax-Exempt Status

COMMENTARY DEI Medical association Press Release Do No Harm Staff

Salt Lake City, UT: October 28, 2026 – Today, Do No Harm expanded its complaint against the American Medical Association (AMA) Foundation concerning the operation of racially discriminatory scholarships in violation of 501(c)(3) requirements, calling on the IRS to investigate the organization’s continued eligibility for tax-exempt status. The addendum to Do No Harm’s earlier-filed complaint presents evidence that multiple scholarships continue to discriminate against medical students based on race and documents the AMA Foundation’s insufficient attempts to address the issues raised in Do No Harm’s original complaint.

“The AMA Foundation has done little to remedy the substantial problems identified in our original complaint regarding its Physicians of Tomorrow program,” said Dr. Kurt Miceli, chief medical officer at Do No Harm. “Months later, race-based scholarships remain in place, having undergone only superficial changes. For one such scholarship, replacing one racial preference with another does nothing to cure the underlying discrimination or end the harm that persists. Moreover, our complaint addendum provides evidence pointing to the Foundation’s reliance on proxies that obscure the continued use of racial preferences. Simply put, these valuable and lucrative scholarship opportunities cannot be awarded based on race. The IRS should include the revised scholarships in any investigation related to Do No Harm’s original complaint and hold the Foundation accountable under federal law, which grants the organization a significant tax advantage at a cost ultimately borne by taxpayers.”

Background

Filed on April 7, 2026, Do No Harm’s original complaint highlighted various AMA Foundation medical-school scholarships that favored certain racial groups over others in violation of 501(c)(3) requirements, which prohibit tax-exempt organizations from engaging in activities contrary to established public policy, including racial discrimination. The scholarships in question initially included the Dr. Richard Allen Williams & Genita Evangelista Johnson/Association of Black Cardiologists Scholarship, which required applicants to be “African American/Black”; the Patricia L. Austin Family Physicians of Tomorrow Scholarship, which restricted eligibility to applicants “of Eastern European descent”; and the Underrepresented in Medicine Scholarship, which limited eligibility to black, Hispanic/Latino, and “Indigenous” applicants.

Within 10 days of Do No Harm’s April complaint, the Foundation quietly removed the discriminatory scholarships in question from its “Physicians of Tomorrow” program website.

However, now, the AMA Foundation has attempted to revise the Austin Scholarship by swapping the previous racial-eligibility criterion for a new one. Instead of a preference for certain European racial groups, the scholarship now states that it gives “preference” to “students who are enrolled members of, or otherwise affiliated with, a federally recognized American Indian or Alaska Native (AI/AN) tribe or group.”

Similarly, although the Underrepresented in Medicine Scholarship now states that it is open to applicants “who come from economically disadvantaged and vulnerable communities and/or demonstrate a dedication to serving vulnerable or underserved populations,” there is evidence that the Foundation is using these facially race-neutral categories as a proxy for prohibited race-based preferences. For example, among other indications, the AMA promotes and plays some role in candidate selection for the Foundation’s Underrepresented in Medicine award and describes it as being “for African American, Latino/Hispanic, or Native Americans/Native Hawaiians/Alaska Natives scholars.”

Click here to read the addendum to our complaint.


Do No Harm, established in April 2022, has rapidly gained recognition and made significant strides in its mission to safeguard healthcare from ideological threats. It has over 50,000 members, including doctors, nurses, physicians, and concerned citizens across all 50 states and 26 countries.

https://donoharmmedicine.org/wp-content/uploads/2022/11/DNH_ContentCards_PressRelease.png 675 1200 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-10-28 10:30:272026-10-28 10:30:27Do No Harm Expands IRS Complaint Calling for Investigation into American Medical Association Foundation’s Tax-Exempt Status
img_16297

Wisconsin Voters to Consider Discrimination Amendment

COMMENTARY Wisconsin DEI Medical School, State government Commentary Do No Harm Staff

This election cycle, Wisconsinites will vote on Question 3, a legislatively referred amendment to the state constitution formally known as the “Prohibit Government Discrimination or Preferential Treatment Amendment.”

The discourse surrounding the question has not been thorough, and additional analysis is warranted.

First the text. Wisconsinites will see the following on their ballots:

QUESTION 3: “Governmental entity discrimination prohibited. Shall section 27 of article I of the constitution be created to prohibit governmental entities in the state from discriminating against, or granting preferential treatment to, any individual or group on the basis of race, sex, color, ethnicity, or national origin in public employment, public education, public contracting, or public administration?”

While both the U.S. and Wisconsin constitutions already mandate legal equality, race-based programs and preferences have continued to exist at the state and local levels of government. The proposed amendment would further strengthen the prohibition on governmental discrimination for any reason.

At stake, as acknowledged by both supporters and opponents, is the ability of Badger State officials to balance disparities by enacting policies that favor certain groups.

State Senator Chris Larson explained his opposition to the amendment in a January press release on the grounds that the amendment would “preven[t] any government program in Wisconsin from … attempting to reverse [the] state’s shameful racial, ethnic, and gender disparities.”

State Senator Stephen Nass has argued for the amendment on strikingly similar grounds: “Past discrimination, however wrong, cannot be corrected with more discrimination. Old Wounds cannot be healed by inflicting new ones.”

However, what has been largely missing from the debate is analysis of how the amendment would affect Wisconsin’s healthcare pipeline, most prominently by impacting which candidates are admitted to the state’s public medical schools.

This is a serious matter. As Do No Harm chronicled last year, black applicants to the University of Wisconsin School of Medicine and Public Health (UWSMPH) had nearly 10 times the odds of admission compared to Asian or white applicants with the same MCAT score and GPA, according to the institution’s 2024 admissions data.

Black students accepted to UWSMPH had an average MCAT score in the 62nd percentile, whereas whites were in the 86th percentile and Asians in the 87th.

Based on that year’s data, the acceptance rate for black applicants to UWSMPH was more than six times greater than that of Asian applicants.

Given the clear link between MCAT scores, medical-school outcomes, and performance on licensing examinations, these elevations of race and ethnicity over academic merit have legitimate public-policy consequences.

At least arguably, Wisconsin is not training the most promising future physicians who knock on its institutional doors.

Badger State voters should consider carefully the specifically medical consequences of Question 3.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2619880101-scaled.jpg 1920 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-10-26 09:10:372026-10-26 09:10:37Wisconsin Voters to Consider Discrimination Amendment
img_16283

How Will Colorado Protect Children?

COMMENTARY Colorado Gender Ideology State government Commentary Do No Harm Staff

Two Colorado ballot initiatives are asking voters to help determine how the state will interact with gender-dysphoric minors.

The first, Proposition 134 (previously Initiative 109), concerns the use of sex-based categories in school sports.

It asks

  • whether “participation in all K-12 and collegiate school sports” should be “based on the participant’s sex” and
  • whether educational institutions must henceforth “designate each school or intramural [team] as male, female, or coeducational” and enforce those designations.

The text of the proposition is worth perusing in its entirety. Debate, however, has largely concerned questions of fairness and safety, values claimed by both opponents and supporters of the measure.

Nadine Bridges, executive director of the LGBTQ+ advocacy group One Colorado, told news outlet Colorado Politics, for example, that the proposition in question is “written … vaguely” and “open[s] the door to unintended consequences that can cause serious harm to all of our kids.”

Proponent organization Protect Kids Colorado, meanwhile, states that “[b]igger, stronger biological males are invading girls’ sports in Colorado, taking away our girls’ dignity, safety, and opportunity.”

Do No Harm adds that male athletic advantage is a physiological finding, not a matter of opinion, as institutions as disparate as the U.S. Supreme Court and the International Olympic Committee now agree.

Differences in lean mass, cardiac output, and skeletal geometry appear before puberty and widen sharply after it, a process affecting not only the respective sexes’ athletic performance on average but also female-athlete safety during competition.

Crucially, published research finds that testosterone suppression narrows but does not close the performance gap, which is why the eligibility question does not resolve itself pharmacologically when female-identifying males undergo hormone therapy.

While the performance capacity of individual male and female athletes will obviously vary, science shows that post-pubescent biological males retain significant physical advantages over biological females.

The second measure, Proposition 135 (previously Initiative 110), would modify existing Colorado law “by prohibiting surgery on a minor for the purpose of altering the minor’s biological sex characteristics.” (The full text, which governs both what healthcare professionals may do and what state or federal funds may pay for, is available online.)

Here, too, both opponents and supporters of the measure lay claim to the mantel of child protection, with Families Not Politics, the One Colorado–led campaign against the measure, maintaining that the change could “interfere with medically necessary care for serious conditions that affect kids well beyond transgender youth” and Protect Kids Colorado pointing to the “irreversible” nature of such procedures.

Important for Colorado voters to keep in mind is that Proposition 135 is about minors’ access to “gender-affirming care.” The measure in question is about age, not the ability of adults to consent to medical procedures performed on their adult bodies.

Systematic reviews commissioned by national health authorities in England, Sweden, and Finland found the evidence for pediatric gender interventions to be weak or of low quality, and each of those health systems has narrowed pediatric transgender practice in response.

Moreover, loss of future fertility is a foreseeable consequence of some of these procedures, and consent doctrine treats such irreversible interventions in minors severely.

Even the terminology attending the debate can teach us something. “Treatment,” a word used often by advocates of pediatric “gender-affirming care,” implies a diagnosis, an endpoint, and a demonstrated benefit.

Both ballot measures have lasting consequences for how children can be protected from potentially harmful activities and interventions.

That is the crux of the matter and the question that Centennial State voters should answer this fall. Colorado voters should take their time to familiarize themselves with these proposals and understand the full implications before casting their ballot.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2803459975-scaled.jpg 1920 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-10-22 12:12:532026-10-22 12:12:53How Will Colorado Protect Children?
Page 1 of 8123›»
COPYRIGHT © DO NO HARM 2026. ALL RIGHTS RESERVED.
  • Contact
  • Privacy
  • Disclaimer
  • Link to X
  • Link to Facebook
  • Link to Instagram
  • Link to LinkedIn
  • Link to Youtube
Scroll to top Scroll to top Scroll to top