• HAVE YOU SEEN OR EXPERIENCED THE IMPACT OF DEI OR RADICAL GENDER IDEOLOGY AT YOUR INSTITUTION? CLICK HERE TO SHARE YOUR STORY.
Do No Harm
  • About Us
    • ABOUT
    • TEAM
    • FAQS
    • WHAT OTHERS SAY
    • VOICES OF DO NO HARM
  • OUR WORK
    • NEWSROOM
    • ISSUE AWARENESS
      • IDENTITY POLITICS (DEI)
      • GENDER IDEOLOGY
    • POLICY WORK
    • LEGAL ACTION
    • RESEARCH
    • RESOURCES
    • CENTERS
  • GET INVOLVED
    • SUBMIT A TIP
    • BECOME A MEMBER
    • CAREERS
    • INTERNSHIPS
    • IMPACT
  • MEDIA INQUIRIES
  • Search
  • DONATE
  • Menu Menu
img_16106

Another Crack in the Pediatric ‘Gender-Affirming Care’ Armor

COMMENTARY Gender Ideology Medical Journal, News Media Commentary Do No Harm Staff

These are bad times to be scaremongering about the mental health of children denied access to so-called gender-affirming care. A new commentary in the social-science journal Theory & Society further demolishes the narrative that such young people are at increased risk of suicidality.

Do No Harm took up this work recently with our new report “The Effect of State Bans on Gender Interventions for Minors on Teen Suicide Rates.”

There, using multiple statistical approaches, including difference-in-differences models and a national time-series analysis, we found no evidence that state laws preventing providers from experimenting on gender-dysphoric children have increased suicide rates in those states.

Now, a new article, “Causal inference from a single treated state: a peer review of Lee et al. (2024) and the exchange that followed,” takes on the widely repeated 2024 claim that so-called anti-transgender laws result in up to a 72-percent increase in suicide attempts among transgender youth.

As M. Lal, author of the new Theory & Society article demonstrates, that particular “finding” fails to stand up under serious investigation.

Predictably, the “72-percent” claim rocketed around the internet shortly after its publication in Nature Human Behavior, in the article “State-level anti-transgender laws increase past-year suicide attempts among transgender and non-binary young people in the USA” by Wilson Y. Lee et al.

The radical LGBTQ+ activist organization the Trevor Project gave the statistic its own webpage and heralded the study as “groundbreaking” and “first-of-its-kind.”

NPR duly repeated the claim, as did PBS, Time, CNN, and a host of other opinion-making outlets.

Earlier this year, the first significant crack appeared in the “72-percent” figure. Responding to the original Nature Human Behavior article in that same journal, J. Cohn et al. pointed out that the Lee study’s headline finding (“up to a 72-percent increase in suicide attempts”) was driven by Idaho alone, despite the fact that the Gem State contributed only a small sample of respondents and had no “anti-transgender” law in effect during the time period in question.

Though Lee et al. publicly acknowledged Idaho’s “prominent role” in their study in the weeks that followed, they insisted that their “choice of statistical approach was appropriate given the nature of the intervention.”

Lal’s innovation in this months’ new Theory & Society article is to show that Lee et al.’s “principal statistical defenses are incorrect.” Indeed, reliance on a single treated state (Idaho) “renders the [original] paper’s reported uncertainty invalid rather than merely fragile,” and “design problems independent of the single-state issue remain unaddressed by the main study or the follow-ups.”

To wit (and in layman’s terms), Lal’s article demonstrates that the headline finding for 13–17-year-olds rests on such a small group of Idaho respondents that changing just four extreme survey responses within that group could move the underlying result by roughly the size of the reported overall effect.

As Lal concludes, the notion that “increasing access to gender-affirming care ‘could be life-saving’ for [transgender or non-binary] young people … is not supported by” the Lee et al. study.

Given the extent to which cant and propaganda govern the talking points of the pediatric transgender lobby, we are unsurprised by the weaknesses of the study to which activists have so often pointed.

What is more startling is the failure of the news outlets mentioned above to retract their coverage or even to append to their articles an acknowledgement of the original study’s flaws.

The arguments for “affirming” young patients’ gender dysphoria with surgeries, hormone therapies, and puberty-blocking drugs are collapsing all around us.

Mainstream news sites ought to report that.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2779891237-scaled.jpg 1709 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-25 16:32:092026-09-25 16:36:10Another Crack in the Pediatric ‘Gender-Affirming Care’ Armor
img_500

Do No Harm Files Comment on Department of Education’s Accreditation Innovation and Modernization Proposed Rule

COMMENTARY DEI Federal government Commentary Executive Do No Harm Staff

Earlier this week, Do No Harm submitted an official comment to the U.S. Department of Education’s Office of Postsecondary Education in response to the department’s notice of proposed rulemaking, “Accreditation, Innovation, and Modernization: The Secretary’s Recognition of Accrediting Agencies.”

Do No Harm supports the proposed rule.

As the rule’s executive summary makes clear, accrediting agencies “serve as key gatekeepers in determining which institutions may participate in … Federal student aid programs, which currently provide more than $100 billion in Pell Grants and Federal student loans annually.”

Sadly, while existing regulations are meant to ensure that recognized accrediting agencies are “reliable authorities regarding the quality of education or training offered by … institutions,” too many accreditors have abandoned this mission, “shifting their focus away from student achievement to compelling institutions to adopt illegal and discriminatory ideology and practices.”

By “eliminat[ing] requirements not required by statute, including the ‘two-year rule’ for initial recognition of new agencies, prescriptive site visit mandates, unnecessary documentation requirements, and rigid and overly long processing timelines,” the new rule would help to spur competition among accreditors and force legacy agencies to return their focus to the quality of the institutions they oversee.

Do No Harm’s support for the new rule is based on four criteria:

First, it lowers federal barriers to recognizing new accreditors and makes it easier for schools to switch accreditors, opening a future path that could diminish incumbent-controlled monopolies that have long dominated medical and healthcare accreditation. Second, it strengthens requirements for accreditor independence from affiliated trade and membership organizations. Third, it returns accreditation to its proper focus on educational quality by barring ideologically driven standards and protecting academic freedom. Fourth, it makes the recognition process faster, fairer, and more transparent.

Please read the full comment here or below.

Do_No_Harm_DOE_Comment_v4
https://donoharmmedicine.org/wp-content/uploads/2022/06/DNH_ContentCards_OfficialComment.png 675 1200 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-23 11:27:102026-09-23 11:27:10Do No Harm Files Comment on Department of Education’s Accreditation Innovation and Modernization Proposed Rule
img_941

Do No Harm Senior Fellow To Chair the United States Preventive Services Task Force

COMMENTARY Department of Health and Human Services Federal government Press Release Executive Do No Harm Staff

Salt Lake City, UT: September 23, 2026 – Do No Harm senior fellow Seth J. Corey, MD, MPH, has been appointed by U.S. Health and Human Services Secretary Robert F. Kennedy, Jr., to chair the United States Preventive Services Task Force. The task force is a “scientifically independent, volunteer panel of national experts in prevention and evidence-based medicine” who work to improve the health of all Americans by reviewing scientific evidence and making recommendations about clinical preventive services.

“We are proud and honored to have Seth appointed to such a prestigious position,” said Stanley Goldfarb, MD, Do No Harm chairman. “Dr. Corey’s clinical expertise and years of experience will prove invaluable for the Preventive Services Task Force. We look forward to seeing the outstanding work he will accomplish on preventive healthcare in America.”

Dr. Corey is a board-certified pediatric hematologist-oncologist in the Departments of Pediatrics and Heart, Blood, and Kidney Research at Cleveland Clinic and the Case Comprehensive Cancer Center and a professor of molecular medicine at Cleveland Clinic Lerner College of Medicine at Case Western Reserve University. He has over four decades of experience providing care for children and young adults and combines clinical expertise with investigative research experience to advance patient-centered, evidence-based care.

Dr. Corey earned his undergraduate degree with honors in biology and the history of medicine from Yale University and his MD and MPH from Tulane School of Medicine and School of Public Health and Tropical Medicine. Following residency at St. Louis Children’s Hospital at Washington University, he completed a fellowship in pediatric hematology and oncology at Boston Children’s Hospital and Harvard Medical School. He completed a post-doctoral fellowship studying cell signaling and metabolism at Tufts University. Dr Corey has coauthored more than 150 original articles, commentaries, and book chapters.

Read Dr. Corey’s full bio here.

Read the HHS announcement here.


Do No Harm, established in April 2022, has rapidly gained recognition and made significant strides in its mission to safeguard healthcare from ideological threats. It has over 50,000 members, including doctors, nurses, physicians, and concerned citizens across all 50 states and 26 countries.

https://donoharmmedicine.org/wp-content/uploads/2022/11/DNH_ContentCards_PressRelease.png 675 1200 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-23 11:18:452026-09-23 11:18:45Do No Harm Senior Fellow To Chair the United States Preventive Services Task Force
img_941

Do No Harm Alleges New Evidence on Planned Parenthood’s Potential Medical-Coding Fraud, Urges HHS to Investigate

COMMENTARY Gender Ideology Department of Health and Human Services Healthcare resource Press Release Executive Do No Harm Staff

SALT LAKE CITY, UT: September 22, 2026 – Today, Do No Harm sent a letter to the U.S. Department of Health and Human Services’ Office of Inspector General (HHS-OIG) raising allegations of a potential nationwide miscoding scheme by Planned Parenthood related to the cross-sex hormones its affiliates prescribe. Do No Harm submitted a formal complaint detailing the evidence and is asking HHS to investigate Planned Parenthood for potential medical-coding fraud.

“Our investigation suggests Planned Parenthood and its regional affiliates may be perpetrating a nationwide miscoding scheme to conceal services for sex-rejecting procedures and to facilitate improper insurance reimbursements for cross-sex hormones,” said Kurt Miceli, MD, chief medical officer at Do No Harm. “We found over a thousand prescriptions for cross-sex hormones that may suggest a failure to use correct diagnosis codes for an associated medical visit. Given our findings and Planned Parenthood affiliates’ history of publicly declaring their use of seemingly spurious codes, it appears the organization may be practicing what it preaches. HHS has the authority and resources to launch a formal investigation into this potentially fraudulent scheme, and we encourage them to do so immediately.”

Background

Do No Harm worked with a private data broker to analyze Planned Parenthood’s coding practices with respect to claims submissions for cross-sex hormone treatments. This investigation involved examining diagnosis codes from medical claims for office visits at Planned Parenthood affiliates and hormone prescriptions where the prescriber was also associated with Planned Parenthood affiliates.

By comparing medical-claim data with prescription-claim data, Do No Harm identified a set of patients who had prescription claims from a Planned Parenthood–related prescriber within 30 days of an office-visit claim at a Planned Parenthood–affiliated facility.

Findings

  • Approximately 5,700 patients aged 22 or younger appear to have received 11,000 to 12,000 gender-related prescriptions from Planned Parenthood affiliates between 2015 and 2025.
  • Of the 5,700 patients, about 800 received 1,100 to 1,200 hormone prescriptions seemingly linked to gender dysphoria but lacking the correct diagnosis codes for the associated office visit.

Call to Action

  1. Do No Harm is asking HHS to further investigate Planned Parenthood affiliates’ coding practices for office visits that lead to prescriptions for cross-sex hormones and other sex-rejecting procedures.
  2. Do No Harm is asking HHS to determine whether and to what extent these miscoded office visits cause pharmacies to fill prescriptions for cross-sex hormones and other sex-rejecting procedures for which claims are submitted to the federal government for reimbursement.

A previous Do No Harm report highlighted how activist groups, including Planned Parenthood, publicly promoted alternative diagnosis codes unrelated to gender dysphoria to facilitate billing and insurance reimbursement for so-called gender-affirming care.

Read Do No Harm’s HHS-OIG Complaint against Planned Parenthood here.


Do No Harm, established in April 2022, has rapidly gained recognition and made significant strides in its mission to safeguard healthcare from ideological threats. It has over 50,000 members, including doctors, nurses, physicians, and concerned citizens across all 50 states and 26 countries.

https://donoharmmedicine.org/wp-content/uploads/2022/11/DNH_ContentCards_PressRelease.png 675 1200 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-22 10:08:272026-09-22 10:08:27Do No Harm Alleges New Evidence on Planned Parenthood’s Potential Medical-Coding Fraud, Urges HHS to Investigate
img_16068

More Youth ‘Gender’ Dominoes Fall

COMMENTARY New York, Pennsylvania Gender Ideology New York University, University of Pittsburgh Health system Commentary Executive Do No Harm Staff

One day, Americans will look back in horror on the irreversible surgeries and pharmacological “treatments” to which ideologues in white coats subjected gender-dysphoric children.

Two new agreements between the Department of Justice (DOJ) and major American healthcare systems bring that day closer.

Last Friday, the DOJ’s Office of Public Affairs announced that deals had been struck to end pediatric sex-rejecting procedures at both New York University Langone Hospitals (NYU) and the University of Pittsburgh Medical Center (UPMC).

These deals follow previous agreements with New York’s Mount Sinai Health System, Texas Children’s Hospital, the Cleveland Clinic Foundation, and Connecticut Children’s Medical Center.

Do No Harm’s full list of hospitals that are pausing pediatric “gender-affirming care” in response to Trump-administration actions is available here.

As part of the new agreements, NYU and UPMC will cease performing “gender”-related surgical procedures on minors and will no longer administer puberty blockers and cross-sex hormones to gender-dysphoric youth.

Additionally, the two organizations will pay fines of $8.5 million and $950,000, respectively.

Announcing the two deals, Attorney General Todd Blanche stated that “[t]he Department of Justice is fighting to protect our nation’s children and working tirelessly to reach agreements with hospitals to end so-called ‘gender affirming care’ for minors.”

Referencing potentially fraudulent billing practices of the kind uncovered in a recent Do No Harm report, Blanche added that the “resolutions send a clear message: hospitals that target children in these practices and then fraudulently obtain payment for the procedures will be held to account.”

As Do No Harm argued in our coverage of the DOJ’s August agreement with Connecticut Children’s Medical Center, these victories belong primarily to the children and adolescents who will not now be subjected to irreversible, life-changing interventions based on a damaging ideology.

Those young people need society’s compassion in the form of forbearance and realism, not hasty, politically charged “medicine” based on falsehoods that activists merely wish were true.

As more and more health systems back down from the radicalism that they previously embraced, keeping children safe from that harm will become easier: Fewer hospitals offering pediatric “gender” “care” means fewer patients allowed to undergo it — or manipulated in that direction.

Yet Do No Harm and its allies can’t afford to relax.

As the DOJ’s press release makes clear, the agreements signed in the last several months proceed in part from President Trump’s 2025 direction that the Department of Justice should “prioritize investigations and enforcement actions involving violations of federal law in the provision of so-called ‘gender-affirming care’ to children.”

What one administration can emphasize, another can halt altogether.

Moreover, a future DOJ led by progressive political appointees might interpret differently (or scrap altogether) the deals that are now being struck.

Simply put, to the extent that hospitals are backing off of pediatric sex-rejecting procedures because of pressure blowing in on the political winds, those gestures are reversible.

What is required in the long term is an American public so well-schooled in the horrors of pediatric “gender-affirming care” that healthcare systems cease offering it of their own volition, permanently.

That day is not yet here, but we believe it is surely coming.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2724002767-scaled.jpg 1694 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-21 11:41:292026-09-21 11:41:29More Youth ‘Gender’ Dominoes Fall
Litigation_Amicus_2

Do No Harm Stands with Parents in Supreme Court Case Challenging Washington Laws Aimed at Transitioning Gender-Confused Runaway Minors

COMMENTARY Washington Gender Ideology State government Commentary Judicial Do No Harm Staff

Later this year, the Supreme Court will hear oral arguments in International Partners for Ethical Care v. Ferguson, which asks whether parents may challenge Washington state laws that shift decisionmaking authority over “gender transitions” from parents to children and the state. Do No Harm eagerly awaits the case’s outcome.  

In our recently filed amicus brief, we further explain the harms the petitioners in the case are seeking to avoid. 

In 2023, the State of Washington enacted legislation designed to provide runaway minors with “gender-affirming treatment” without parental knowledge or consent. Despite this novel transfer of power from parents to their children and the state, and its clear violation of parents’ constitutional rights to direct the care and upbringing of their children, the Ninth Circuit ruled that the plaintiffs lacked standing to challenge the relevant Washington laws. 

Behind these questions of standing lies a grim reality. The petitioners in this case are the actual parents of children with gender dysphoria but believe in the binary, biological reality of sex. They reasonably fear that, if they enforce their beliefs too sternly, their children will run away and use Washington’s laws to receive sex-denying interventions without parental consent.  

Too often, courts overlook exactly what such interventions entail, as proponents of so-called gender-affirming care bury the details beneath a mountain of euphemisms. Our brief attempts to correct this oversight, explaining in forthright terms why the harm the petitioners seek to avoid is indeed a grave one.  

To begin with, sex-denying interventions involve the physical manipulation and disfigurement of young bodies through medical and surgical means — all to treat a psychological condition (gender dysphoria) that has no corresponding physical symptoms.  

Second, sex-denying interventions frequently cause significant long-term negative health consequences in gender-dysphoric youth, as Do No Harm has previously explained.  

Third, recent medical evidence belies the notion that sex-denying interventions are justifiable treatments for gender dysphoria in children. In fact, recent evidence shows that such “treatments” may even exacerbate gender dysphoria’s psychological symptoms.  

In sum, the harms from which the petitioners in this case seek to shield their children are damaging interventions falsely disguised as support and care.  

Unfortunately, as multiple Justices have more recently observed, the question of legal standing is becoming an excuse for some federal courts to avoid contentious constitutional questions. Do No Harm looks forward to the Court’s resolution of these important issues.

https://donoharmmedicine.org/wp-content/uploads/Litigation_Amicus_2.jpg 631 1101 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-18 08:00:172026-09-16 16:59:56Do No Harm Stands with Parents in Supreme Court Case Challenging Washington Laws Aimed at Transitioning Gender-Confused Runaway Minors
img_941

Do No Harm Report Debunks Claim That State Restrictions on Pediatric Sex-Rejecting Interventions Increase Adolescent Suicide Rates

COMMENTARY Gender Ideology State government Press Release Do No Harm Staff

Salt Lake City, UT: September 17, 2026 – Today, Do No Harm released a study finding no evidence for the widespread and alarmist claim that state prohibitions on surgeries, puberty blockers, or cross-sex hormones for gender-dysphoric minors increase suicide rates.

The study, titled “The Effect of State Bans on Gender Interventions for Minors on Teen Suicide Rates,” examines the claim that state bans on so-called gender-affirming care for minors lead to spikes in suicides. Employing three distinct analytical models, Do No Harm found no evidence to support the claim.

“The alarmist claim that protecting children from sex-rejecting procedures increases suicide is false,” said Jay Greene, Director of Research at Do No Harm. “We examined the evidence in a first-of-its-kind study of how teen suicide rates were affected by states adopting policies restricting so-called gender-affirming care for children. No matter how you examine the data, the result is consistently clear: These state policies did not increase teen suicide rates. Medical practice and policy must be grounded in evidence, not emotionally manipulative talking points. That principle is all the more critical when it’s a matter of children’s health and well-being.”

Do No Harm’s Three Models:

  • Difference-In-Difference Model: a statistical method comparing trends across states before and after policy changes. After accounting for national suicide trends, state economic conditions, and suicide rates among young adults, Do No Harm found a 0.3-percent reduction in suicides among 15–19-year-olds, a statistically insignificant change.
  • Callaway and Sant’Anna Difference-In-Difference Model:a newer statistical method designed to provide more reliable estimates when states adopt policies at different times. Do No Harm’s results were unchanged, showing no impact of bans on gender interventions for minors on suicide rates among 15–19-year-olds.
  • National Time-Series Model:analyzed monthly national suicide data among 13–17-year-olds to assess whether expanding prohibitions on sex-rejecting interventions for minors affected youth suicide rates. After controlling for age-adjacent suicide trends, seasonality, economic conditions, and national time trends, Do No Harm found no relationship between these policy changes and teen suicide rates.

Do No Harm’s study also debunks the flawed research cited by activists, media, and lawmakers to justify the suicide myth and claiming that “gender-affirming care” is “lifesaving.” These studies have profound methodological limitations and depend on unreliable evidence.

Read Do No Harm’s study here.


Do No Harm, established in April 2022, has rapidly gained recognition and made significant strides in its mission to safeguard healthcare from ideological threats. It has over 50,000 members, including doctors, nurses, physicians, and concerned citizens across all 50 states and 26 countries.

https://donoharmmedicine.org/wp-content/uploads/2022/11/DNH_ContentCards_PressRelease.png 675 1200 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-17 10:08:572026-09-17 10:08:57Do No Harm Report Debunks Claim That State Restrictions on Pediatric Sex-Rejecting Interventions Increase Adolescent Suicide Rates
img_16030

We’re Breaking Through

COMMENTARY DEI Medical Journal Commentary Do No Harm Staff

Part of Do No Harm’s work of highlighting and counteracting divisive trends in medicine is talking to audiences whom we don’t always reach.

For an organization that means to help shape the conversation around “Diversity, Equity, and Inclusion” (DEI) and youth-focused gender ideology, breaking through to new readers couldn’t be more crucial.

We’re proud to share some of our recent excursions into new territory. Do No Harm’s ideas are landing, and we’ll be partnering with our members and allies to keep up the good work.

• The recent Washington Post article “How Trump administration threats could affect medical school admissions” spends much of its time quoting the talking points of “diversity” proponents — for example, Association of American Medical Colleges chief executive David J. Skorton, who announced in a 2023 webinar that “[l]ives depend on us successfully diversifying the health care workforce.”

Yet the article also quotes our own Ian Kingsbury, senior director of Do No Harm’s Center for Accountability in Medicine, in support of the Trump administration’s efforts to force medical schools to comply with the Supreme Court’s Students for Fair Admissions v. Harvard decision:

Every data point that we see speaks to continued and really pervasive discrimination within medical school admissions. […] As Pres. Reagan famously quipped, “When you can’t make them see the light, make them feel the heat.”

• Bloomberg, too, recently quoted one of our experts. In “Trump Asks DOJ to Probe Hospitals Over Trans Health Coding,” Do No Harm’s chief medical officer, Kurt Miceli, MD, explained that “gender ideologues are able to misuse medical diagnosis codes to avoid proper reporting and scrutiny and to enable potentially fraudulent billing practices.” Thus did Dr. Miceli share the central theme of our April report on that subject.

• Miceli also wrote letters to the editor at Neurology and JAMA Network Open earlier this year, making the case in both instances that unscientific narratives of structural injustice are shifting attention away from the proper practice of medicine and medical education. Miceli in Neurology: “Patients would be better served by a roadmap tackling neurologic disease, not political agendas.”

• Miceli’s contributions to STAT and KevinMD do similar work, urging physicians to focus on patients rather than advocacy. An excerpt from the latter is illustrative: “Diverting attention toward broad policy agendas risks diluting medicine’s core mission and for that we will all inevitably suffer.”

• Do No Harm’s Jay Greene, director of research, published his own JAMA Network Open letter earlier this year, explaining why a recent examination of racial disparities in black and white mortality rates suffers from methodological and interpretive problems. “[T]he evidence presented,” Greene writes, “does not sufficiently support the claim that systemic discrimination, via stress pathways, directly shortens lives in Black communities.”

These incursions into new territory matter. Too often, readers of mainstream publications have never heard an authoritative, evidence-based case against the progressive narratives and policy preferences that have come to dominate the American medical establishment.

To the extent that we’re storming those gates, we’re setting ourselves up for even more wins down the road.

That’s news we’re happy to make happen — and to share.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_1715523877-scaled.jpg 1708 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-15 09:07:302026-09-15 09:07:30We’re Breaking Through
img_500

Do No Harm Files CMS Comment on the American Medical Association and Medical Coding

COMMENTARY, Uncategorized DEI, Gender Ideology American Medical Association, Centers for Medicare and Medicaid Services Federal government, Medical association Commentary Executive Do No Harm Staff

Earlier today, Do No Harm submitted an official comment to the Centers for Medicare & Medicaid Services (CMS) in response to the agency’s formal reconsideration of the relationship between the American Medical Association (AMA) and the medical coding standards that define clinical practice.

We support this inquiry and urge CMS to treat its Request for Information as the beginning of necessary reform rather than the end.

Federal regulation has long entrenched a single private association’s monopoly over the code set that defines physician services, and the revenue that flows from that monopoly is neither spent for the benefit of patients nor answerable to the physicians the AMA claims to speak for. That alone justifies the agency’s decision to ask these questions and to keep pursuing the answers.

This state of affairs is exacerbated by the fact that the AMA spends freely on political advocacy, using its medical authority to inappropriately prop up its activism.

Patients and the public need a payment system built on codes that align with medical necessity rather than on a copyright that funds activism. Thus, CMS is right to have opened this question, and the answer should not be the current, damaging status quo.

Please read the full comment here or below.

DNH Comment CMS Payment Systems Rule2 9-2026
https://donoharmmedicine.org/wp-content/uploads/2022/06/DNH_ContentCards_OfficialComment.png 675 1200 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-11 18:25:202026-09-11 18:25:20Do No Harm Files CMS Comment on the American Medical Association and Medical Coding
img_16003

Politics in the Therapy Session

COMMENTARY DEI American Psychological Association Professional organization Commentary Do No Harm Staff

Once upon a time, therapists took care to hide their ideological views from their patients, presenting instead a “blank screen” that allowed the therapeutic relationship to function as intended.

Mark that down as one more casualty of the Age of Wokeness.

Elizabeth Bernstein’s recent Wall Street Journal article “Is Your Therapist Biased? Personal Agendas Are Creeping Into the Therapy Room” provides a useful entrée for the curious reader.

According to Bernstein, more and more therapists have begun to “push their own ideologies, encourage patients toward a path that worked for them, and even judge family members they have never met.”

Bernstein mentions therapist and former professor William Doherty, who argues that “many therapists are getting caught up in trends in both therapy and the culture, including the encouragement of victimhood, estrangements and the broadening of terms like ‘harassment’ and ‘abuse.’”

While Bernstein offers tips for prospective and current therapy-seekers (e.g., “Beware if [mental-health professionals] diagnose someone not in the room”), the reader gets the decided impression that the problem is becoming ingrained.

As clinical psychologist and psychology professor Joel Weinberger tells Bernstein, “It used to be that you didn’t tell your patient your personal view or orientation … [b]ut now there is this view that you do, because you’re sharing good values.”

This ongoing alteration of the therapeutic dynamic is not the first time that politics and ideology have intruded into the field of psychology.

As recent (and not-so-recent) students know, academic psychologists have embraced “liberation psychology,” “decolonial psychology,” and “climate psychology” for years, substituting vogue political grievances for such evidence-based therapeutic modalities as cognitive behavioral therapy.

Commenting on this trend in 2023, Chapman University’s Richard E. Redding remarked that the “political views of psychologists can and frequently [do] color and skew their teaching and research.”

That skew is what we’re observing today: Old-fashioned depression is out; “climate anxiety” is in.

Or consider the output of the American Psychological Association (APA), whose 2017 “Multicultural Guidelines” mention “privilege” and “oppression” more than 40 times each, with “social justice” appearing nearly a dozen times (and nearly a dozen more in the “References” section).

To the extent that therapists allow APA priorities to shape their practices, they will increasingly offer care along progressive ideological lines rather than on the basis of carefully gathered evidence.

Do No Harm covered this phenomenon recently. As we wrote last month, a number of mental-health professionals have begun advertising themselves as fellow activists and openly broadcasting their ideological priors (e.g., “I practice from a feminist and anti-oppressive perspective”).

So much for the blank screen: An activist therapist treating activists is almost certain to affirm when he or she ought to challenge, speak when he or she ought to be silent, or feed patients’ anxieties or delusions when he or she ought to alleviate them.

Sadly, we seem to be moving beyond the age of the apolitical therapist whose focus was on patient well-being, not mutual congratulation or complaint.

For the sake of the profession and patients, we should hope for a return to that standard.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2492805193-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-10 11:08:572026-09-10 11:08:57Politics in the Therapy Session
img_15989

The APA’s ‘Inclusive Language Guide’ Hasn’t Helped

COMMENTARY DEI American Psychological Association Professional organization Commentary Do No Harm Staff

Future historians hoping to understand the Age of Wokeness will turn gratefully to the American Psychological Association’s “Inclusive Language Guide.” As a marker of progressive ideological anxiety and complaint, the 51-page document may be impossible to top.

Updated in 2023, the guide is intended by the APA to “dismantle the destructive hierarchies that have marginalized people from equitable representation and participation in society.”

So confident is the association that “certain terms are harmful to marginalized communities” that it includes a preemptive apology of its own: “We … understand that some of the terms and concepts that are included [in the guide] may be offensive and painful to different groups.”

What is this potentially debilitating language? A number of the words and phrases listed in the opening “General Terms Related to Equity and Power” section have long been a part of the American and international political conversation (e.g., “antisemitism”). Others have been popularized more recently, as theoretical academic discourse has filtered down to newspapers, magazines, public-radio broadcasts, and K-12 classrooms (e.g., “cultural competence”).

None are in any way provocative.

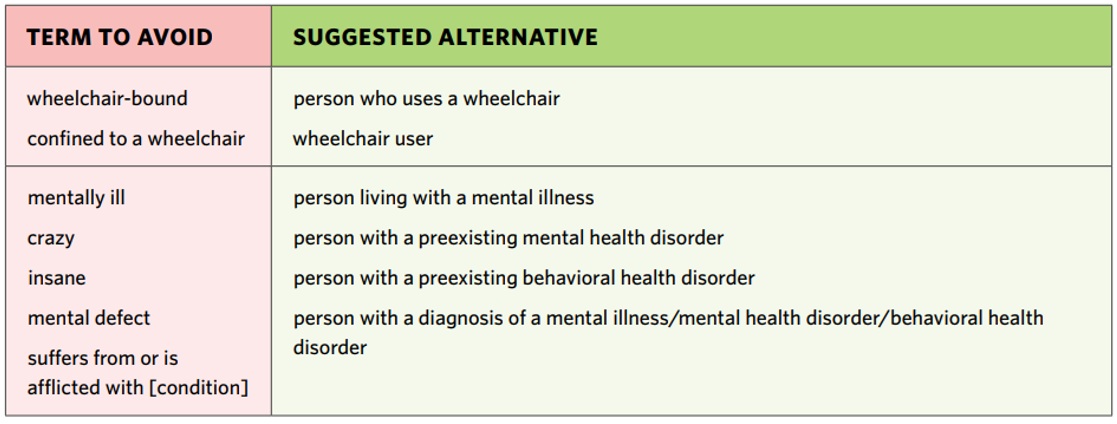
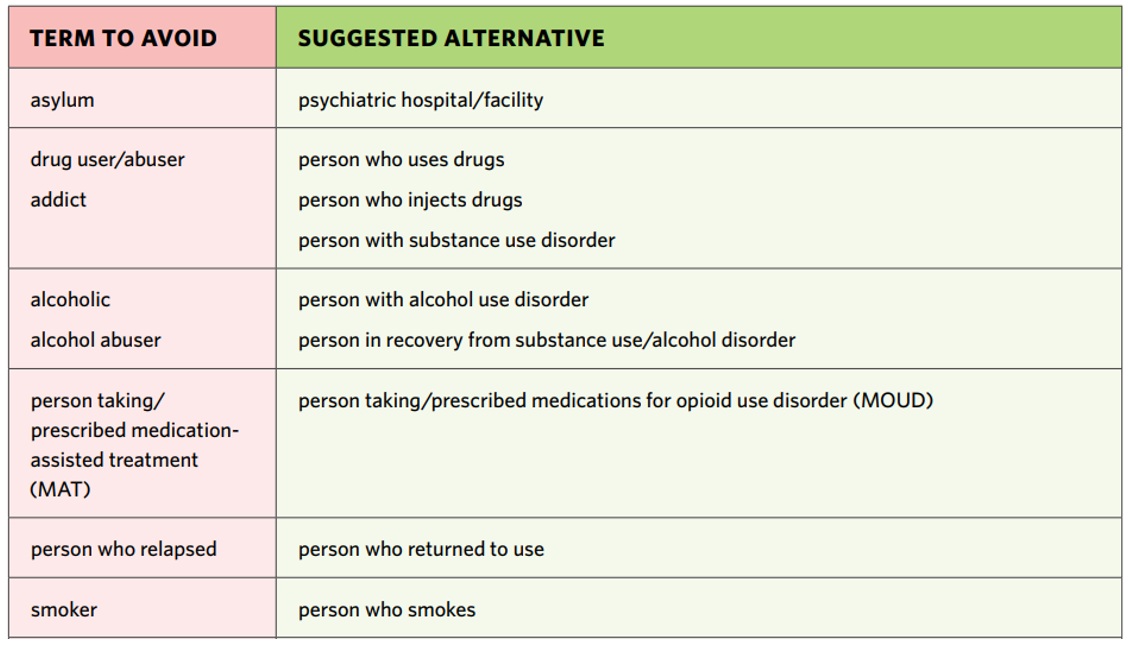
Or perhaps the APA has in mind the allegedly harmful language listed on an accompanying “Term to Avoid” / “Suggested Alternative” chart. There, for instance, readers learn that one ought not to say “mentally ill” when what one really means (or should mean, anyway) is “person living with a mental illness.”

Readers learn that, e.g., “smoker” is no longer in vogue. The preferred linguistic alternative is now “person who smokes.”

We linger on this point because the APA’s exaggerated fear of giving offense is at the heart of its Inclusive Language Guide’s intellectual misjudgments. The document’s very foundation is the unfalsifiable (and therefore unscientific) belief that delicate terminology somehow improves the lot of racial, ethnic, and religious minorities and the physically and mentally handicapped (apologies: we mean “persons with disabilities”).

Because this premise is irredeemably flawed, those committed to it have no choice but to search farther and farther afield for “acceptable” alternatives, as yesterday’s preferred terms inevitably become today’s rank abuse.

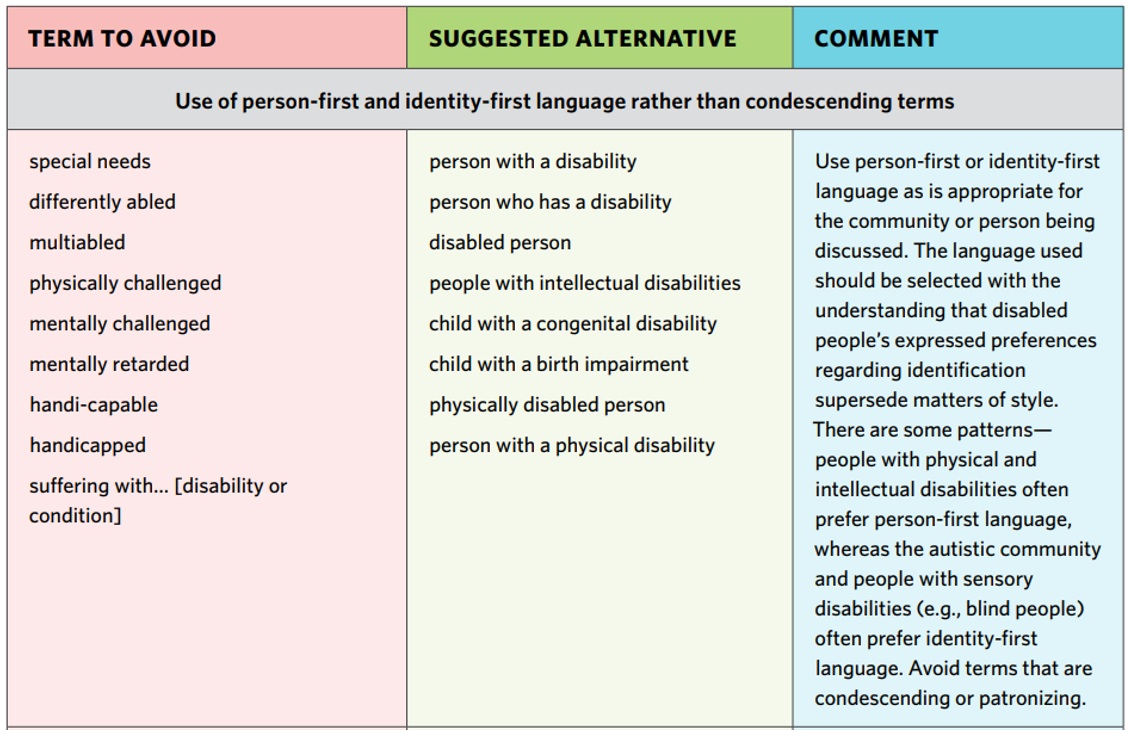
Consider, for example, the troubled career of “differently abled,” a phrase that once represented the height of good taste but is now one of the APA’s explicitly named “term[s] to avoid.”

Without question, that phrase has lost its stylishness. To argue that it is actively offensive, however, is to engage in unserious intellectual contortions. It is moral preening, not the mitigation of harm — clubbishness, not profitable advice.

Indeed, one gets the decided impression, reading the APA’s document, that the point is to create and maintain a clerisy rather than to look out for the needs of those whom the APA ostensibly wishes to help. All but the most uncouth members of society know that the phrase “mentally retarded” ought not to be used in polite company. Yet only an elite few know that “special needs” is now outré, as well. Thus does the APA maintain its professional exclusivity.

To be sure, the consequences of this way of thinking are sometimes comic. When, in January 2023, the Associated Press tweeted that writers ought not to “dehumanize[e]” their reporting subjects by referring to, e.g., “the poor, the mentally ill, the French, the disabled, [or] the college-educated,” the French Embassy to the United States jokingly suggested changing its name to the “Embassy of Frenchness in the US.”

“Handi-capable,” another verboten term as of the APA’s 2023 update, was, from the moment of its origination, a seeming parody of woke cluelessness.

Perhaps the APA is right to remind its members and site visitors to “[a]void terms that are condescending or patronizing,” as the final image above declares. Certainly all speakers and writers should treat others with respect.

There is a fine line, however, between that project and the policing of normal, harmless words. In its pursuit of progressive social outcomes, the APA has left that border far in the rear-view mirror.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2495355841-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-08 15:59:202026-09-08 15:59:20The APA’s ‘Inclusive Language Guide’ Hasn’t Helped
img_15981

Behavioral and Biological Factors Related to Perinatal Cardiometabolic Risk

COMMENTARY DEI Medical Journal Commentary Kurt Miceli, MD

[Editor’s note: This piece originally appeared as a comment in response to “Intersectional Inequities in Age-Related Risk of Adverse Maternal Cardiometabolic Health,” published in JAMA Cardiology. That article can be read here.]

Elleni Hailu et al. observe that black women are at increased perinatal cardiometabolic risk compared to white women with that risk rising more steeply with age. Their discussion offers a list of theorized interpretations including “structural racism,” “experiences of racism,” “racism-related stress,” “chronic discrimination,” “bias and neglect in health care settings,” & “eco-social theory,” which as per Nancy Krieger, who introduced the term decades ago, “rejects the underlying assumptions of biomedical individualism.”

Yet, individual behavioral & biological factors should be considered to better understand the paper’s observation. Physical activity, diet, & cholesterol, along with genetics, all contribute to cardiovascular (CV) health. Every day of unmanaged risk factors worsens insulin resistance & arterial stiffness, for example, thereby compounding risk with age.

Read the full comment in JAMA Cardiology. 

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2393940895-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-08 09:00:402026-09-08 09:01:20Behavioral and Biological Factors Related to Perinatal Cardiometabolic Risk
img_15976

The American College of Obstetricians & Gynecologists Should Abandon Ideology

COMMENTARY DEI, Gender Ideology Medical association Commentary Do No Harm Staff

If one ever needed proof that medical associations are subject to institutional capture by activists, the American College of Obstetricians & Gynecologists (ACOG) provides it.

Boasting 62,000 members, ACOG is, according to its own materials, “the leading professional membership organization for ob-gyns.”

The association states that it provides “comprehensive, expert-reviewed practice guidelines” to its members and that those practitioners “maintain the highest professional standards and are united in their delivery of exceptional, respectful, science-backed care for patients.”

Yet these encouraging pledges are joined on the same webpage by ACOG’s commitment to “equitable” care, a now-familiar indicator of politicization.

Moreover, the organization’s self-defined mission is to “support our members to improve the lives of all people” — not women — “seeking obstetric and gynecologic care.”

That particular word choice is explained on ACOG’s “Inclusive Language” page, which argues that “[v]aluing, respecting, and affirming an individual’s identity contribute to improved health outcomes.”

Later on the same page, the association declares, “To be inclusive of women and all patients in need of obstetric and gynecologic care, ACOG will move beyond the exclusive use of gendered language and definitions.”

Do No Harm notes with alarm the irreconcilability of the organization’s commitment to “science-backed care” and its assertion that “all people” may benefit from gynecologic medicine. (We concede that gynecologists may occasionally treat biologically male patients for sexually transmitted infections or screen biological men for anal cancer, but that has been the case since well before ACOG’s revision of its mission-statement language. The revision is about transgenderism.)

We note, furthermore, that ACOG’s policies and practices impact not only adult patients but minor children.

Among ACOG’s resources is a committee opinion titled “Health Care for Transgender and Gender Diverse Individuals,” which explicitly concerns both adults and adolescents and which directs site visitors to the radical World Professional Association for Transgender Health (WPATH) “[f]or guidance on the medical and surgical care of transgender adolescents.”

Elsewhere, on its “Adolescent Health” page, ACOG advocates for “privacy and the ability of adolescents to consent to health-care procedures” and argues that “education about … gender … empowers and prepares children, adolescents, and young adults to make educated decisions about their health and their relationships.”

Simply put, the organization’s embrace of transgender ideology is not limited to the “adult” corner of its operations. Minors, too, are necessarily implicated in ACOG’s woke “gender”-related ideas.

On the matter of DEI, the association is little better. As its “Diversity, Equity, and Inclusive Excellence at ACOG” page makes clear, the organization believes it “essential that the culture of our organization, membership, leadership, and fellowship be diverse, equitable, inclusive, and just.”

A “Collective Action Strategy” page condemns the “racial inequities present in our field,” while a statement of policy titled “Racism in Obstetrics and Gynecology” argues that “[r]acism has been and continues to be systemically embedded into our society and the practice of medicine.”

Echoing the totalism to which ideological progressives often fall prey, the second of those pages insists that “[r]acial and ethnic inequities in obstetrics and gynecology cannot be reversed without addressing all aspects of racism and racial bias, including the sociopolitical forces that perpetuate them” (emphasis added).

So much is wrong with these claims that one hardly knows where to begin. Most obviously, they substitute unfalsifiable, quasi-magical forces (“systemic racism”) for matters that physicians are equipped to address (e.g., patient behavior and medical discovery).

They encourage doctors to engage in policy work outside of their realms of expertise, thus lending the authority of medicine to policy prescriptions that may not be reasonable or practical.

Most importantly, they compromise the aforementioned standard of “science-backed care” to which ACOG pledges itself and to which all medical associations should be held.

Happily, the solution to these problems lies in plain sight: ACOG should depoliticize its activities and webpages and return to the irreplaceable business of providing evidence-based obstetric and gynecologic care to women and girls.

Do No Harm joins all who oppose the politicization of medicine in eagerly awaiting such a move.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_1898831023-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-04 14:50:252026-09-04 14:52:58The American College of Obstetricians & Gynecologists Should Abandon Ideology
img_15972

How Monopolistic Accreditors Enforce Ideology

COMMENTARY DEI American Psychological Association accrediting organization Commentary Stanley Goldfarb, MD

[Editor’s note: This piece originally appeared as a letter to the editor in response to “Busting the ABA’s Accreditation Monopoly,” published Aug. 29 in the Wall Street Journal.]

The American Bar Association unfortunately isn’t alone in having an accreditation monopoly (“Busting the ABA’s Accreditation Monopoly,” Review & Outlook, Aug. 29). The same is true for many other organizations, including the American Psychological Association Commission on Accreditation, whose status as an accreditor is now up for renewal. Like the American Bar Association, the American Psychological Association is a professional association with an in-house accreditation arm. And, like the ABA, the APA temporarily suspended its DEI standards in 2025. But suspension isn’t the same as removal, and the Education Department is right to see to it that these standards are eliminated, as has been done by accreditors for schools of medicine, podiatry and optometry.

Read the full piece in the Wall Street Journal.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2633916331-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-04 12:36:502026-09-04 12:36:50How Monopolistic Accreditors Enforce Ideology
img_941

Do No Harm’s Center for Accountability in Medicine Releases Second Medical School Rankings Based on Excellence and Merit

COMMENTARY DEI Medical School Press Release Do No Harm Staff

SALT LAKE CITY, UTAH: September 3, 2026 – Today, Do No Harm’s Center for Accountability in Medicine (CAM) released the second edition of its Medical School Excellence Index.

The Medical School Excellence Index is the only definitive ranking of U.S. medical schools based on their commitment to academic excellence, transparency, and opposition to divisive identity politics. The Index offers prospective medical students, medical schools, residency programs, and other interested parties an alternative to the traditional rankings systems that often favor schools with DEI programs or ignore their detrimental effects.

“We created the Medical School Excellence Index so that patients and aspiring medical school students have clear information about which schools are doing the best job of recruiting and training physicians,” said Ian Kingsbury, PhD, Senior Director of the Center for Accountability in Medicine. “Since launching the Index last year, we’ve seen several schools change their mission statements and applicant essay prompts in ways that eschew DEI-aligned activism. Unfortunately, we’ve also seen some backsliding by schools that infuse DEI into admissions and student grading policies. As we continue to make progress to restore excellence to medical education, this tool will be invaluable to the public and students who want medical schools to focus on training the next generation of highly qualified medical professionals.”

The Medical School Excellence Index was launched last year and is updated annually. It identifies the best and worst medical schools in the country by ranking each institution on three criteria: academic excellence, transparency, and the rejection of DEI.

Top 5 Medical Schools:

  • USF Health Morsani College of Medicine
  • Albert Einstein College of Medicine
  • Perelman School of Medicine at the University of Pennsylvania
  • Dell Medical School – University of Texas at Austin
  • Vanderbilt University School of Medicine

Bottom 5 Medical Schools:

  • Michigan State University College of Human Medicine
  • Charles R. Drew University of Medicine and Science College of Medicine
  • California University of Science and Medicine – School of Medicine
  • University of California, Riverside School of Medicine
  • Roseman University College of Medicine

The full rankings can be found here.


Do No Harm, established in April 2022, has rapidly gained recognition and made significant strides in its mission to safeguard healthcare from ideological threats. It has over 50,000 members, including doctors, nurses, physicians, and concerned citizens across all 50 states and 26 countries.

https://donoharmmedicine.org/wp-content/uploads/2022/11/DNH_ContentCards_PressRelease.png 675 1200 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-03 10:12:032026-09-03 10:12:03Do No Harm’s Center for Accountability in Medicine Releases Second Medical School Rankings Based on Excellence and Merit
img_15956

A ‘Do-It-Yourself’ Hormone Website May Be Catering to Gender-Dysphoric Children

COMMENTARY Gender Ideology Federal government, Healthcare resource Commentary Executive Do No Harm Staff

Earlier this year, Do No Harm released a report demonstrating the ease with which minors may be able to purchase sex-rejecting pharmacological agents on the internet.

While some of the websites we mentioned appear to have since shut down, our more recent trips across the web indicate that gender-dysphoric children can still access inappropriate advice and supplies.

Take, for example, the website diyhrt.wiki. (The acronym stands for “do it yourself hormone-replacement therapy.) Visitors to the site need only click a button attesting “I am 18 or older” to gain access to the main page.

From there, anyone who wishes may view such subpages as “Transmasc Guide,” “Transfem Guide,” and “Injection Supplies.”

Lest anyone be confused, the last of those pages opens with a note: “All the links for injection needles are for 1 inch needles intended for intramuscular injection. Please consider using 0.5 inch needles if you wish to inject subcutaneously.”

And what will the self-professed “adults” in question be putting into their bodies? The homepage makes it clear: “This website intends to teach transgender people how to safely perform DIY Hormone Replacement Therapy.”

Websites of this kind are among those to which we drew attention in our March report, “The Lack of Barriers to Minors Ordering Cross-Sex Hormones Online.”

Included in our findings were a number of resources directing users to online pharmacies, distribution networks for “homebrew” hormones, and guides on self-administering cross-sex hormones once one has secured them.

Diyhrt.wiki is exactly this sort of project. In addition to providing sources for “pharmaceutical grade” hormones, the site links to “Homebrew Sourcing” involving the international shipping of, e.g., estradiol injections and transdermal gels.

(Note: Vanna Pharma appears at least temporarily to have closed. Otokonoko Pharmaceuticals’ URL has changed, but the site is easily searchable and relies on an effortlessly bypassed age-verification self-assessment.)

The site also offers advice (e.g., “Is this illegal?” and “What do I do if my package is seized?”) and tells “transfem” and “transmasc” site visitors what levels of estradiol and testosterone to aim for.

Perhaps most disturbingly, it advises secrecy among its users, some of whom could be underage given the absence of meaningful gatekeeping.

“Share the site with those who need it, but not to transphobes: use common sense!,” the homepage warns.

If your package is seized, “do not tell customs what is inside the package.”

Such winking and nodding appears to be a concession to the fact that Americans of any age shouldn’t be buying prescription drugs online without a valid doctor’s order. (Additionally, more than half of states have enacted laws specifically limiting minors’ access to “gender-affirming care.”) Yet the behavior being promoted is not only legally questionable but dangerous on its face.

Because vendors of “homebrew” hormones exist to allow customers (including minors) to bypass legal restrictions on sex-denying interventions, they necessarily sidestep oversight by the Food and Drug Administration (FDA), thus exposing children to unknown risks.

This is unsafe, offers no benefits, and must be stopped.

The FDA should continue investigating online pharmacies selling unprescribed hormones, including the “homebrew” variety.

Moreover, individual states should investigate and prosecute unlawful online sellers to the extent permitted by law. Indeed, new legislation may be necessary if vendors continue circumventing state restrictions on cross-sex hormones for minors.

Finally, U.S. Customs and Border Protection should exercise its legal authority to inspect inbound international cargo as circumstances warrant. “A trans woman in Brazil” should not be providing American children with “medicine” cooked up on “her” kitchen stove.

What we are calling for is common sense. Children mustn’t have unprescribed access to pharmacological agents, and websites that facilitate that access must be shut down.

That solution may not be politically easy, but we should aim for it nonetheless.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2807213251-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-09-02 15:16:352026-09-02 15:16:35A ‘Do-It-Yourself’ Hormone Website May Be Catering to Gender-Dysphoric Children
img_15937

An Activist Physician Is Spreading a Debunked ‘Racism’ Narrative

COMMENTARY Wyoming DEI Medical School Commentary Do No Harm Staff

A popular narrative blaming racism for black maternal health disparities has been the subject of debunking efforts for years. Nevertheless, a top advocate of that conspiracy theory remains a celebrated speaker, writer, and continuing medical education (CME) contributor.

Later this week, Joia Crear-Perry, MD, will serve as keynote speaker at the inaugural Wyoming Maternal Health Summit, sponsored by the University of Wyoming College of Health Sciences’ Rural Health Institute.

Crear-Perry’s remarks will contribute to the summit’s theme, “Closing the Distance: Maternal Health Access and Innovation in Wyoming,” and will consider the alleged “challenges Wyoming faces” including “systemic factors driving preventable maternal deaths.”

In one sense, Crear-Perry is an obvious choice for such an event, having founded the National Birth Equity Collaborative (NBEC), a “nationally recognized organization on the front lines of the Black maternal health & infant mortality crises.”

Yet the “highly sought-after trainer & speaker” is, in another sense, a strange and disappointing choice. The theory of systemic racism and black maternal mortality that she advances relies on bad science and a misunderstanding of statistical data.

Do No Harm staffers have done much of the necessary debunking ourselves.

Whereas Crear-Perry argues that “Race Isn’t a Risk Factor in Maternal Health. Racism Is,” we demonstrate that having a doctor of the same race doesn’t improve patients’ healthcare outcomes.

Whereas Crear-Perry’s NBEC states that, “[i]n comparison to other high-income countries, the U.S. has the highest maternal … mortality rates despite the most healthcare spending, & [that] most of these deaths are preventable,” we explain that the U.S. rate may result from a reporting system that overestimates maternal deaths and whose metrics are not fully comparable to those of other developed nations given how deaths are ascertained.

Whereas Crear-Perry blames “exposure to racism” for the alleged fact that “Black women in the United States are the most likely of this country’s women to die from pregnancy-related complications,” we show that such a claim diverts resources from proper channels in an attempt to address “a nonexistent factor in poor health outcomes.”

Moreover, we explain how activists have traditionally misinterpreted the CDC data that undergird the systemic-racism theory of black maternal mortality. To wit,

it’s hard to draw society-wide conclusions from such a small sample. It’s even harder when you recognize that the CDC statistics include deaths that occurred up to a year after delivery, as well as those caused by underlying and preexisting medical conditions that pregnancy may have aggravated. And the CDC admits that the systems for identifying mortality rates are prone to error.

Given the flaws in her argument, Crear-Perry ought not to be the fêted and “highly sought-after” medical “expert” (read: activist) that contemporary racial anxieties have made her. Alas, her work as a speaker, educator, and medical celebrity is going smashingly.

In addition to her upcoming Wyoming address, Crear-Perry has participated in a CME opportunity offered to physicians by the American Medical Association. In that video session, “Prioritizing Equity: The Root Cause,” Crear-Perry contends that “[r]acism, classism, and gender oppression” are the “root causes” not only of health inequities but of “most all inequities in the United States of America.”

Crear-Perry has been celebrated in a 2021 Lancet article, “Joia Crear-Perry: collaborating for racial and reproductive justice,” which boasts that she “works on ‘reframing the conversation’ about race to develop a ‘shared vocabulary and understanding of why health inequities exist’ because ‘it’s really racism that is causing the harm.’”

We will not argue that there is any insincerity in Crear-Perry’s “racism” theorizing. She very clearly believes what she preaches.

And let’s also be clear: Maternal mortality is a serious matter deserving of thoughtful, evidence-based study. As Do No Harm has previously written, policymakers and the medical community ought to be focusing their efforts on better hospital training programs for responding to complications and greater use of prenatal care, not looking around every corner for alleged physician bias.

Yet it is just as obviously the case that the woke takeover of the medical establishment has made Crear-Perry’s message irresistible, never mind its poor basis in science.

Crear-Perry’s fame, in other words, is a mere symptom. The widespread — indeed, the “systemic” — eagerness to embrace progressive ideological narratives in medicine is the disease.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2500167131-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-08-31 17:53:382026-08-31 17:53:38An Activist Physician Is Spreading a Debunked ‘Racism’ Narrative
img_15942

Children With Gender Dysphoria Deserve Real Treatment

COMMENTARY Gender Ideology Federal government Commentary Executive Kurt Miceli, MD

[Editor’s note: This piece originally appeared as a letter to the editor in response to “Medicaid and Transgender Treatments for Kids,” published Aug. 18 in the Wall Street Journal.]

Your editorial “Medicaid and Transgender Treatments for Kids” (Aug. 18) correctly notes that public funding will continue to support the mental-health needs of children with gender dysphoria after the Trump administration’s recent rule change for Medicaid and the Children’s Health Insurance Program. Funds through those programs simply can no longer go to puberty blockers, hormone therapies or gender surgeries for minors. This is good news. Let’s hope that in general mental-health services stop perpetuating the “affirmative” model of care that has already led so many children to use these irreversible, invasive medical practices.

Read the full piece in the Wall Street Journal.

https://donoharmmedicine.org/wp-content/uploads/shutterstock_2599292677-scaled.jpg 1707 2560 Do No Harm Staff https://donoharmmedicine.org/wp-content/uploads/DNH_Logo_Stethescope-1.png Do No Harm Staff2026-08-31 16:35:092026-08-31 16:35:09Children With Gender Dysphoria Deserve Real Treatment
Page 2 of 7‹1234›»
COPYRIGHT © DO NO HARM 2026. ALL RIGHTS RESERVED.
  • Contact
  • Privacy
  • Disclaimer
  • Link to X
  • Link to Facebook
  • Link to Instagram
  • Link to LinkedIn
  • Link to Youtube
Scroll to top Scroll to top Scroll to top